Egypt Masterclass · 1,200 Physicians
The Science · Dr. Roberto Amore

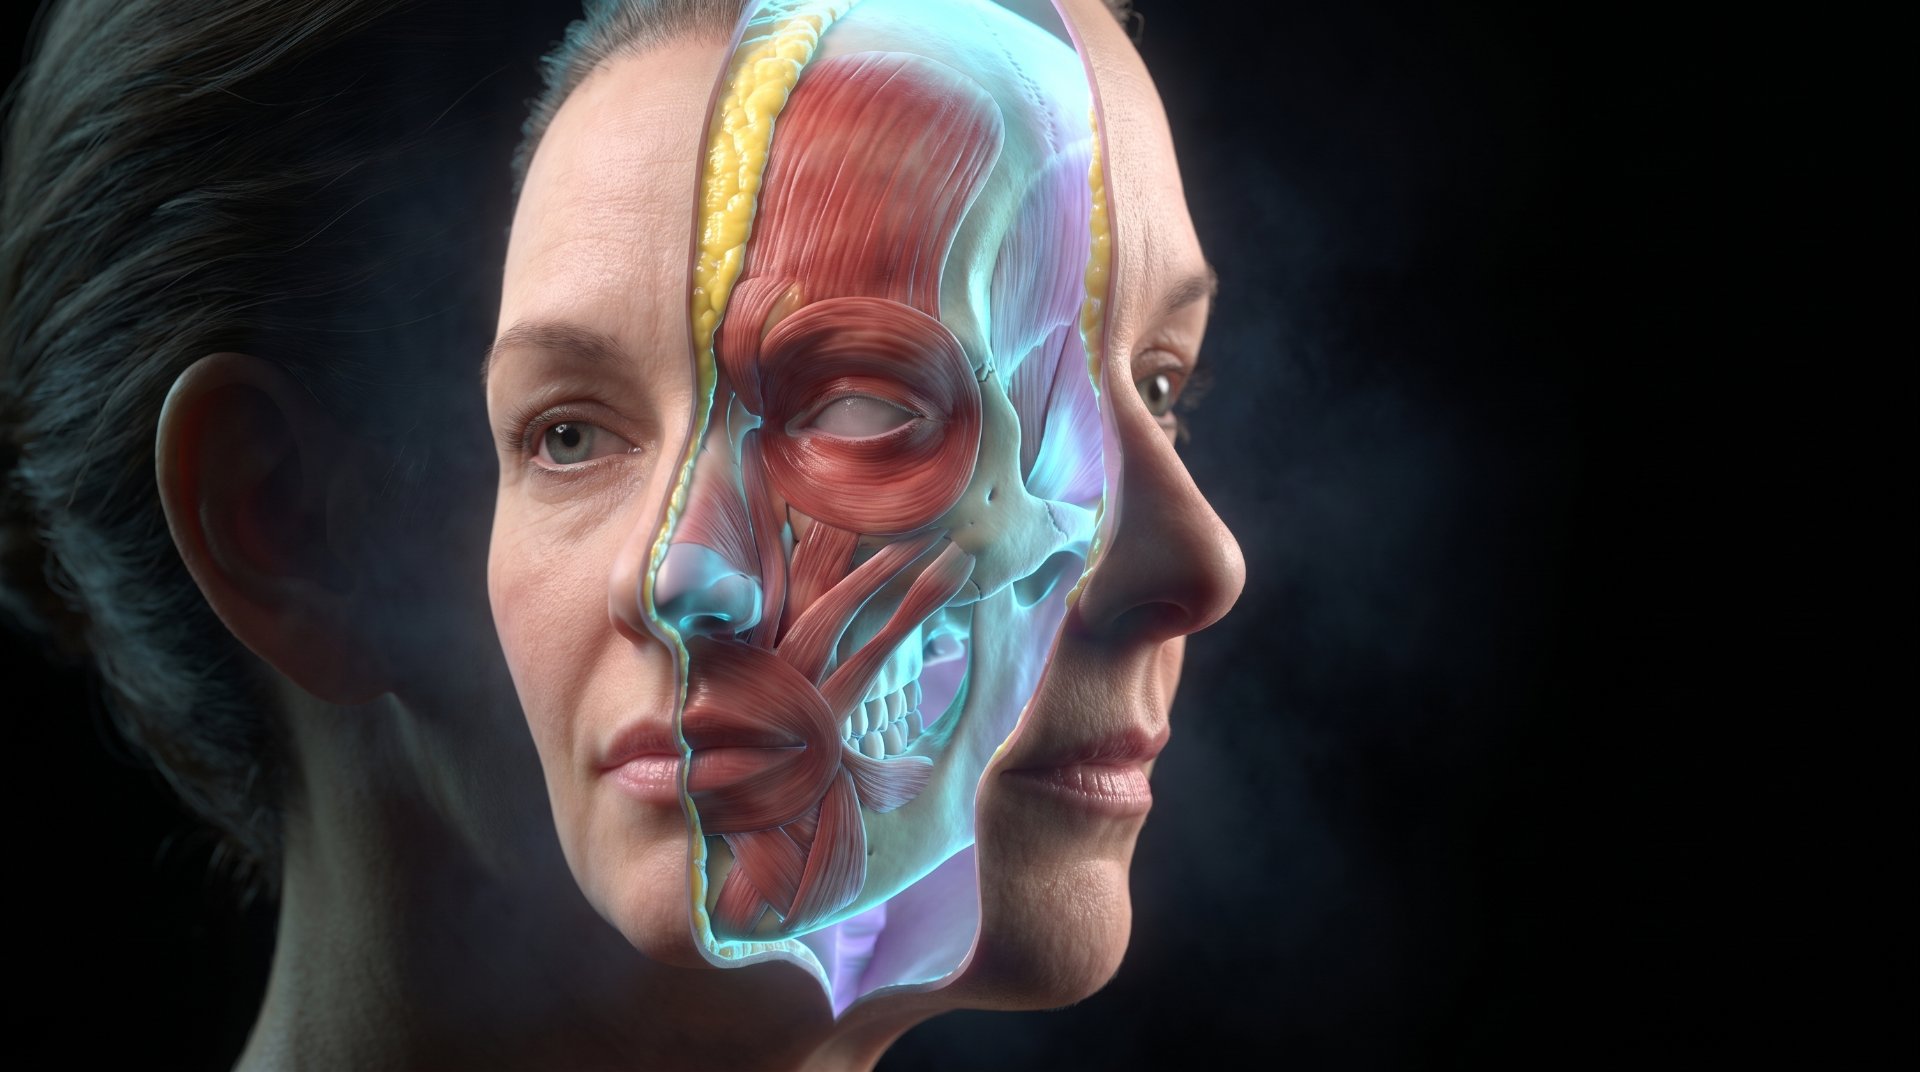
The face doesn't only lose volume. It loses structure.

Aging is a cascade through every layer at once. One product cannot answer it with one mechanism.
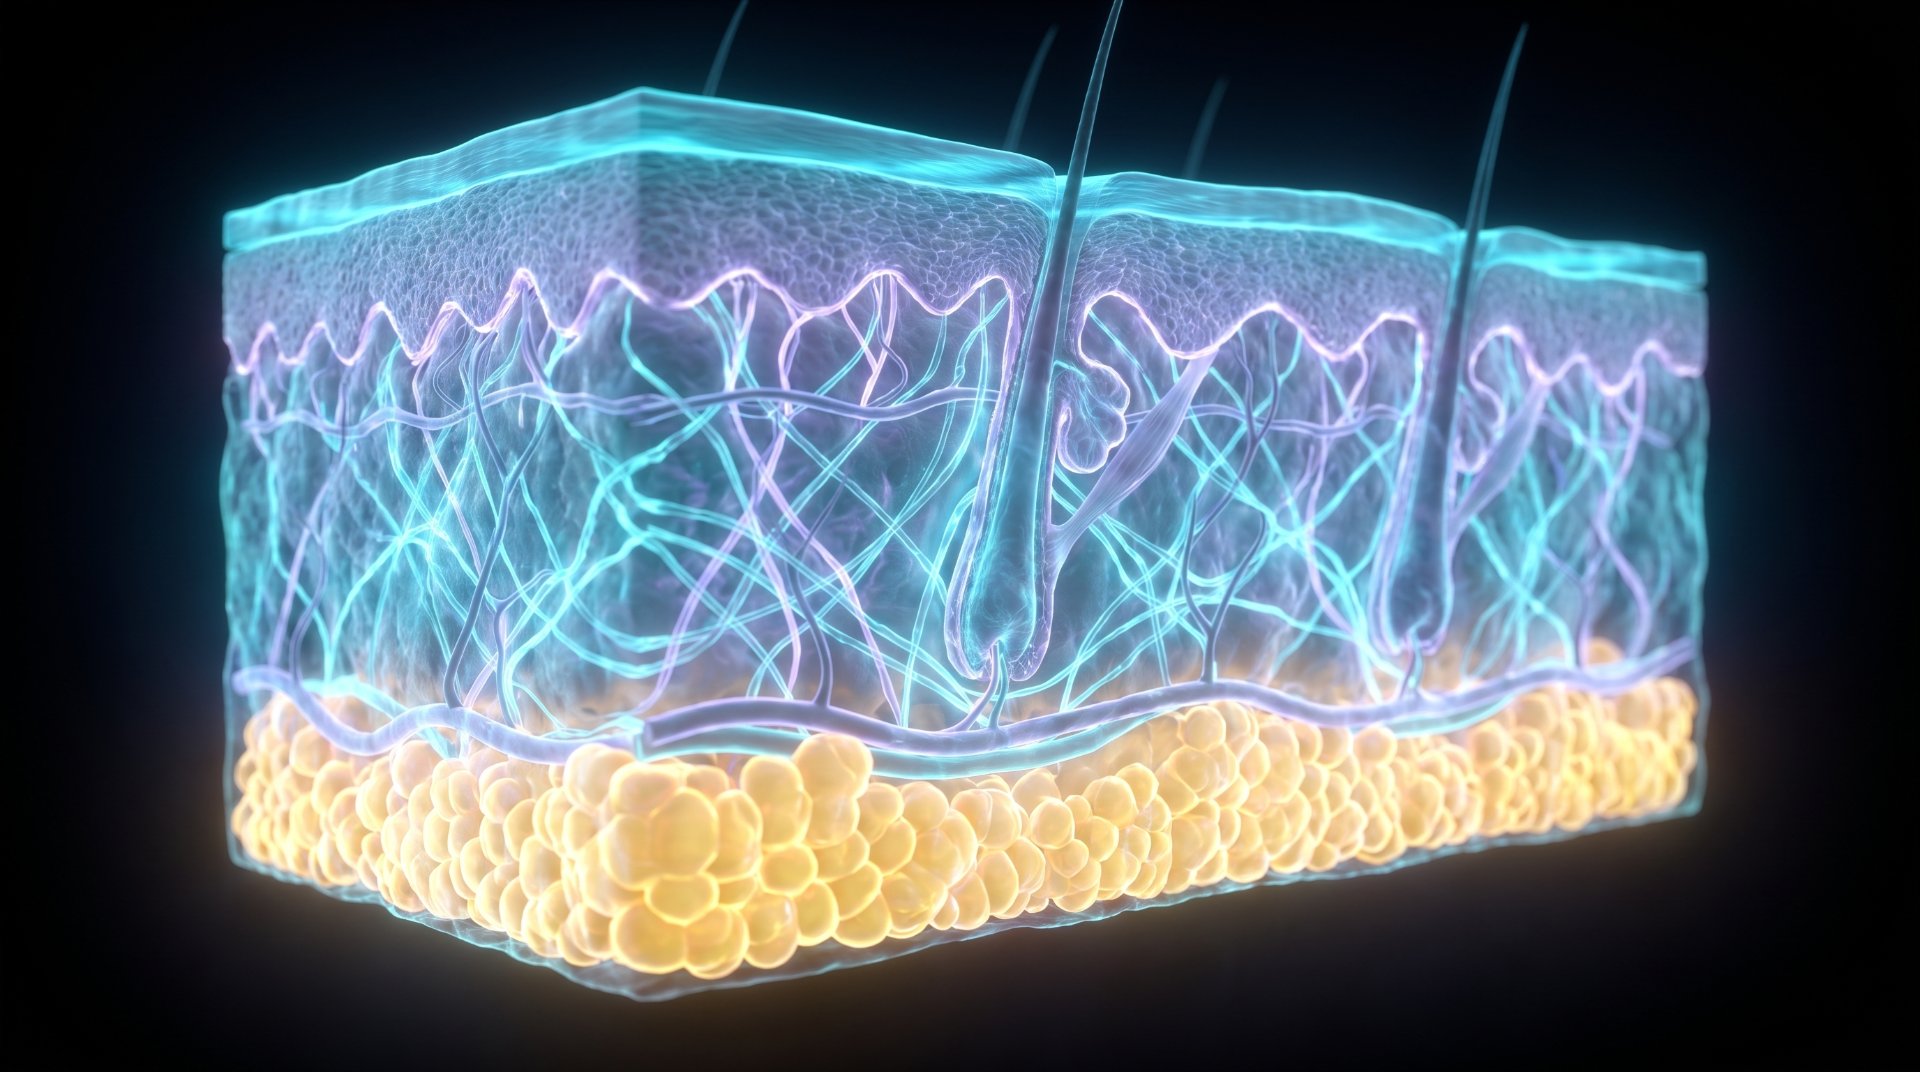
The aging cascade

Four layers, one decline

  • Bone resorbs and the facial frame retreats
  • Fat pads deflate and descend
  • Ligaments lose their hold
  • Dermis thins as collagen and hydration fall
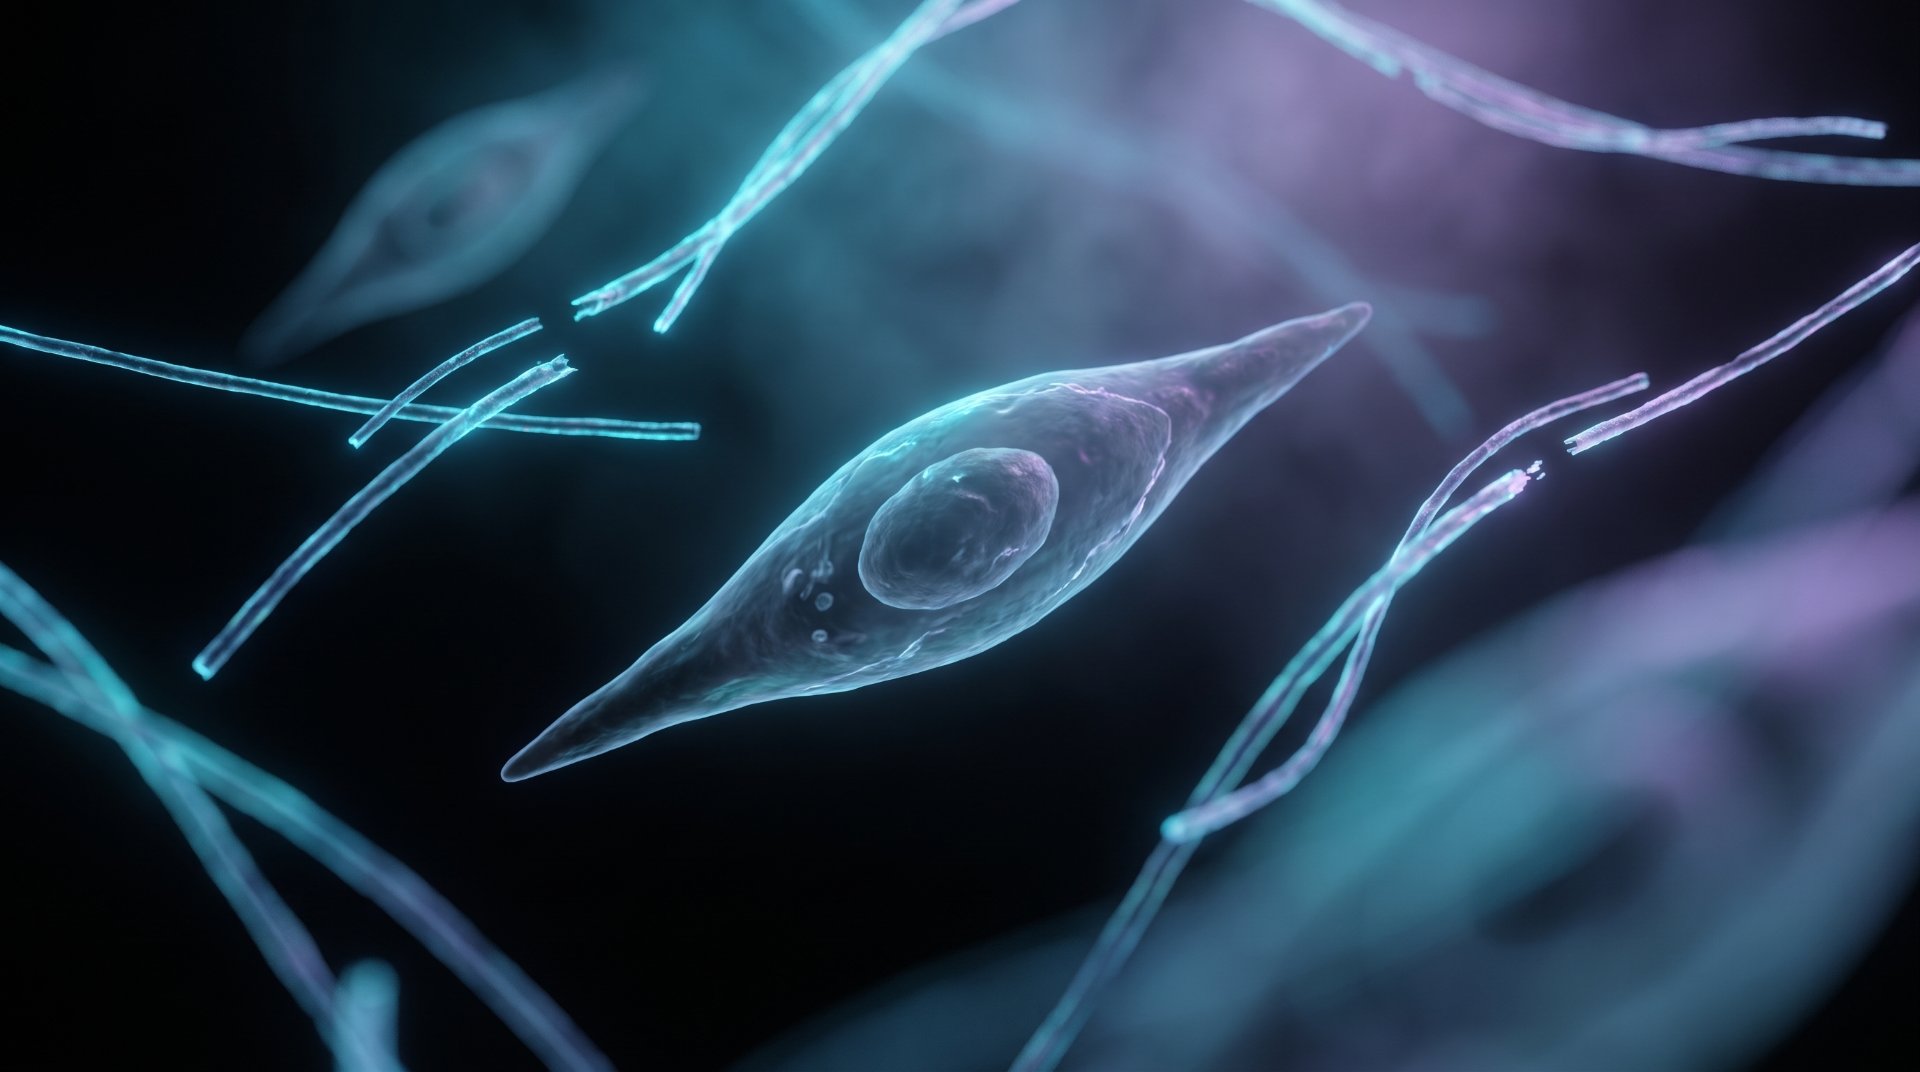
Meet the target cell

The fibroblast, asleep

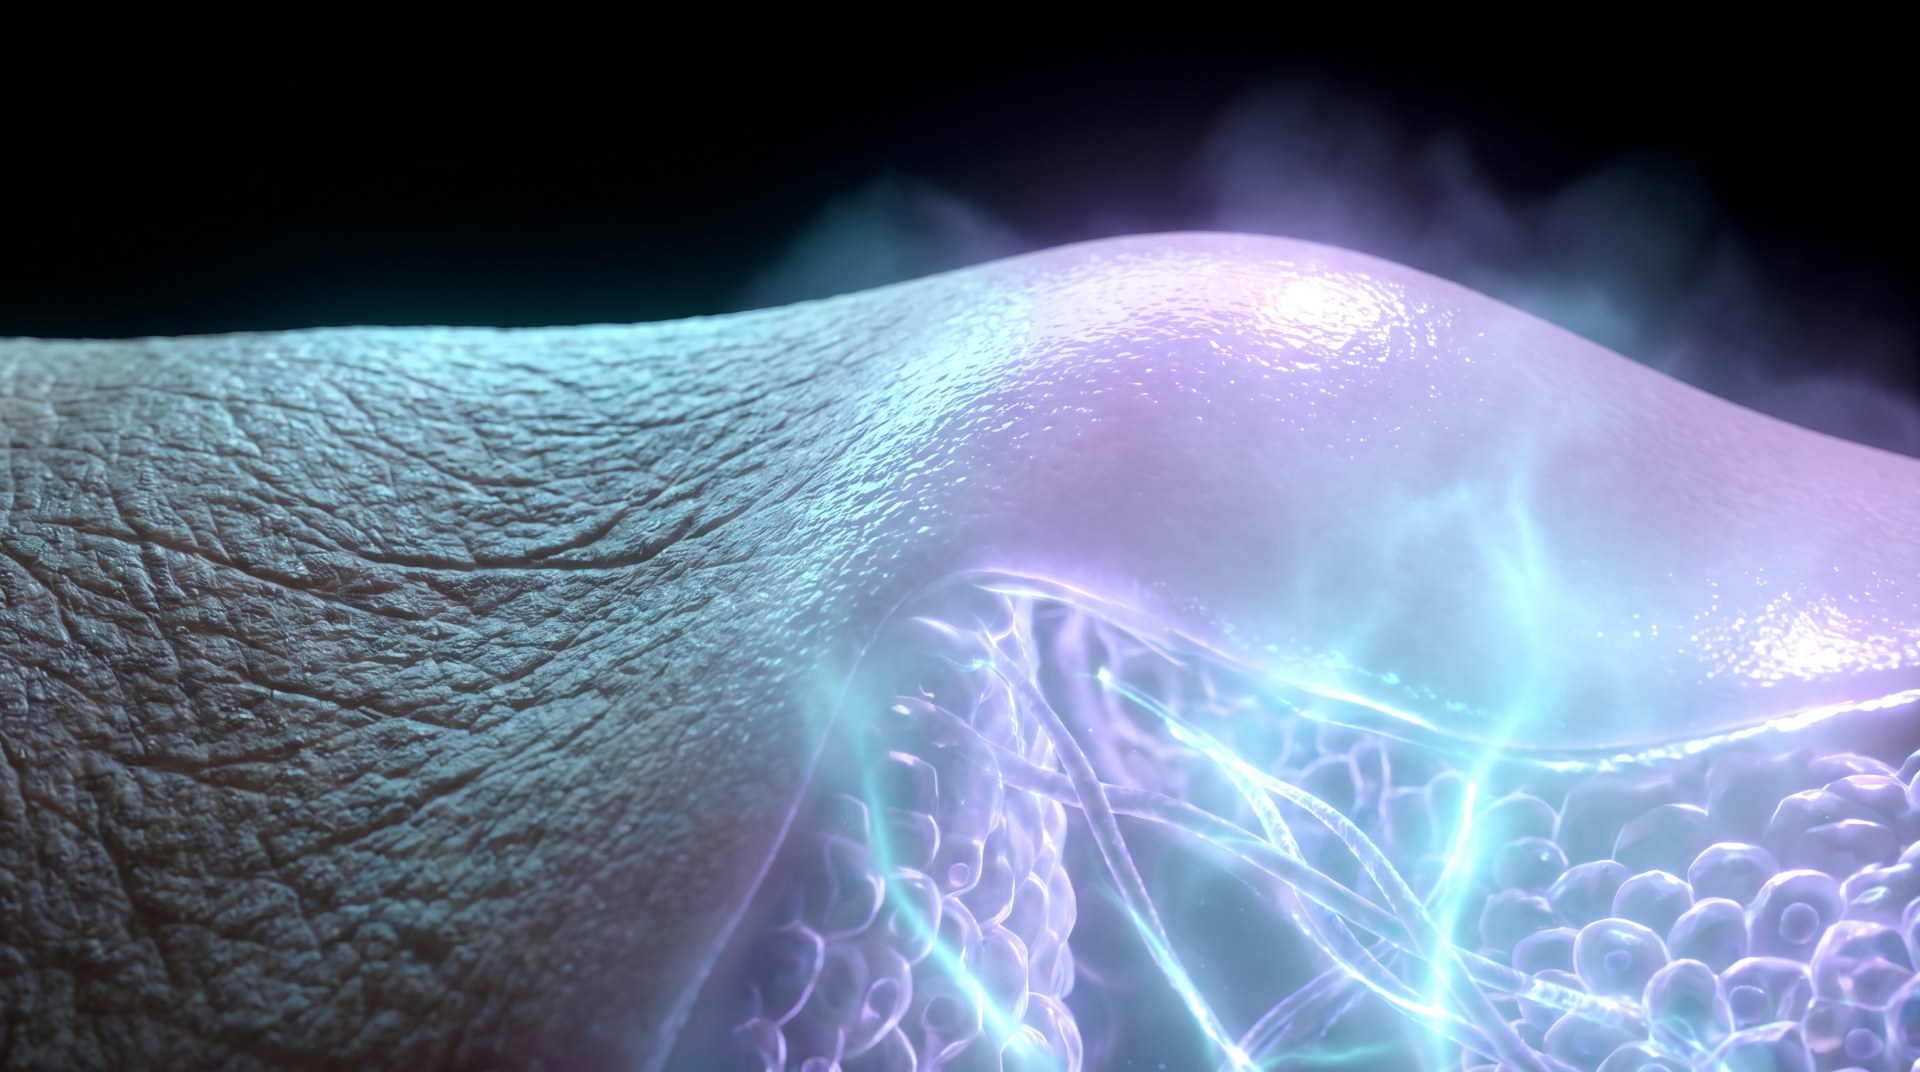
With age, fibroblasts lose mechanical tension and slow their collagen output. The matrix around them loosens and breaks.

Biostimulation

Give it a scaffold, and it wakes up

Stretched over a stable surface, the fibroblast returns to building type I collagen and elastin.
Hyaluronic acid

Fills now

Binds water. Gives immediate volume, lift and hydration from the first minute.
Calcium hydroxylapatite

Builds next

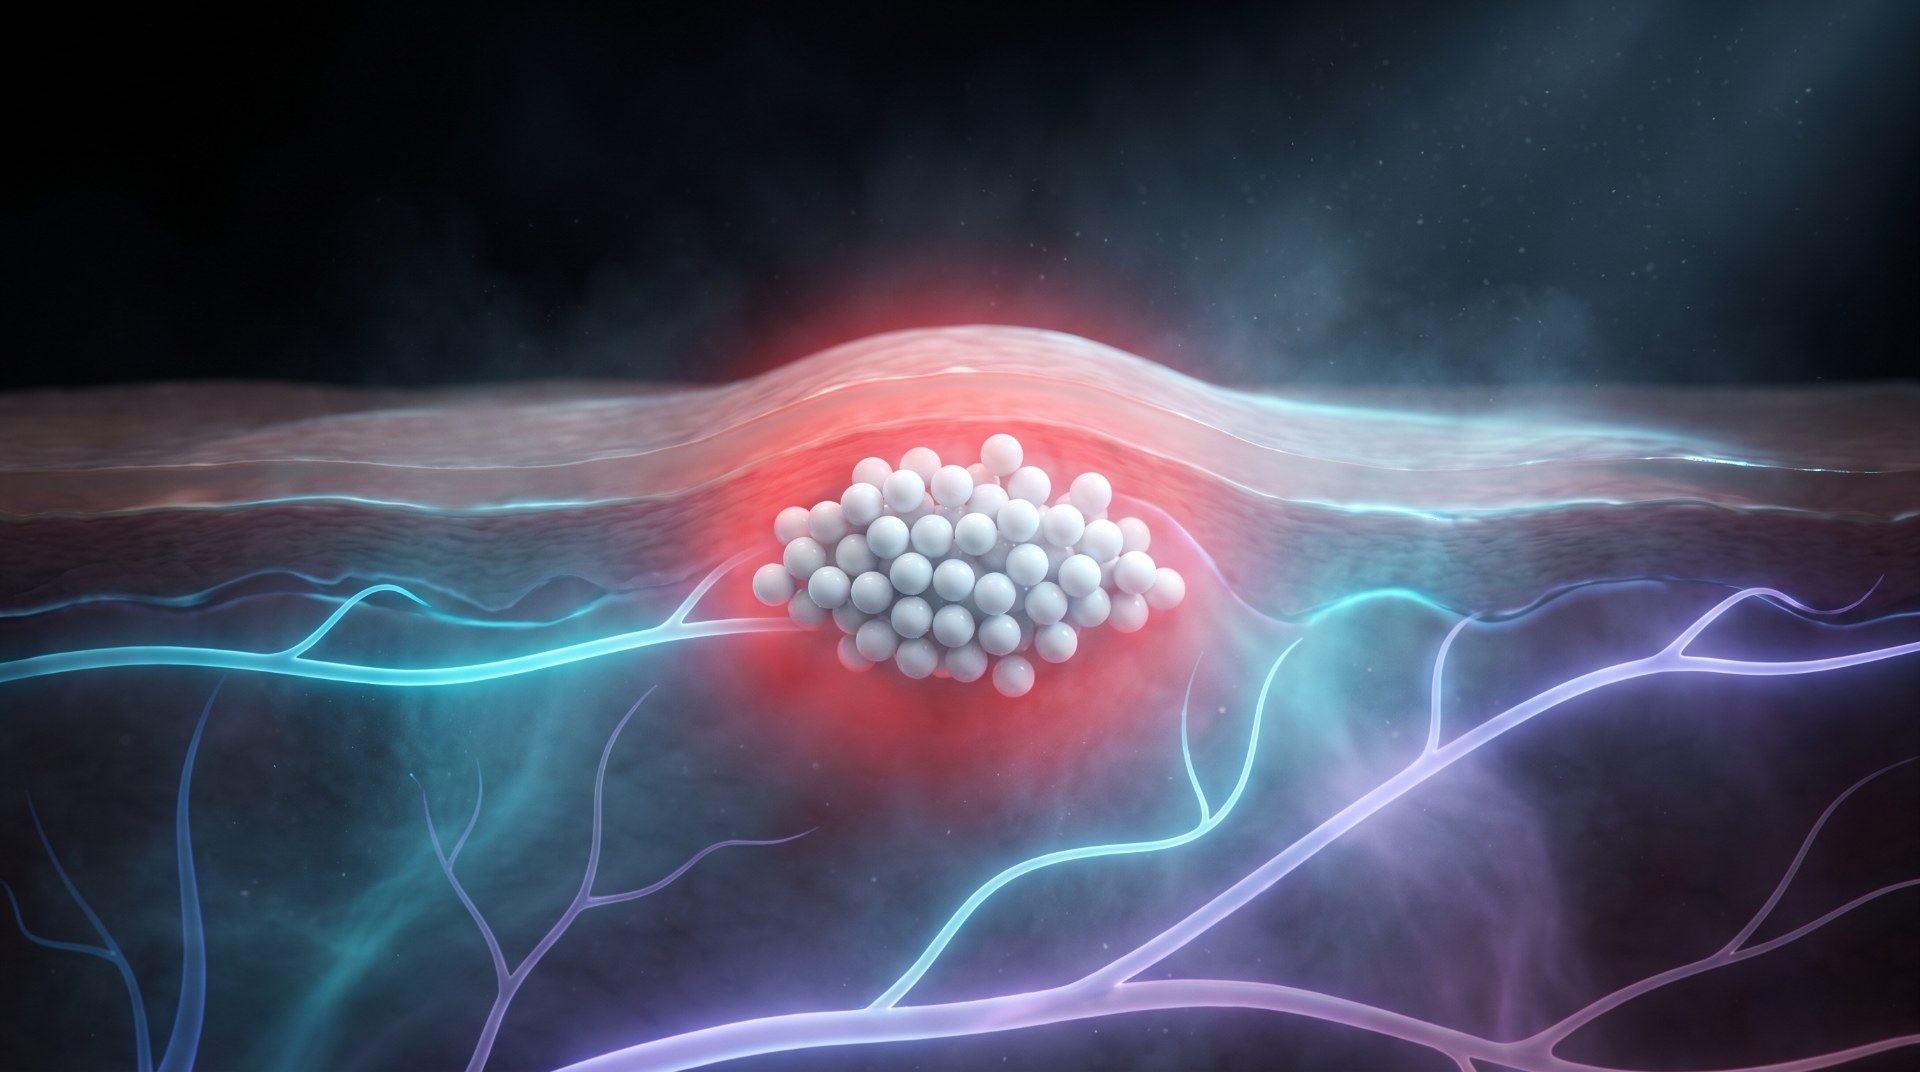
Microspheres act as a scaffold for fibroblasts. New collagen forms over the following months.
Why hybrid is the new standard

From filling to regenerating

  • Patients now ask for natural, progressive change, not a "filled" look
  • One injection does two jobs: correction today and biostimulation over months
  • The HA phase gives the injector immediate visual feedback while the CaHA works
  • Structure and skin quality in one treatment plan
The hybrid concept

Immediate result. Living result.

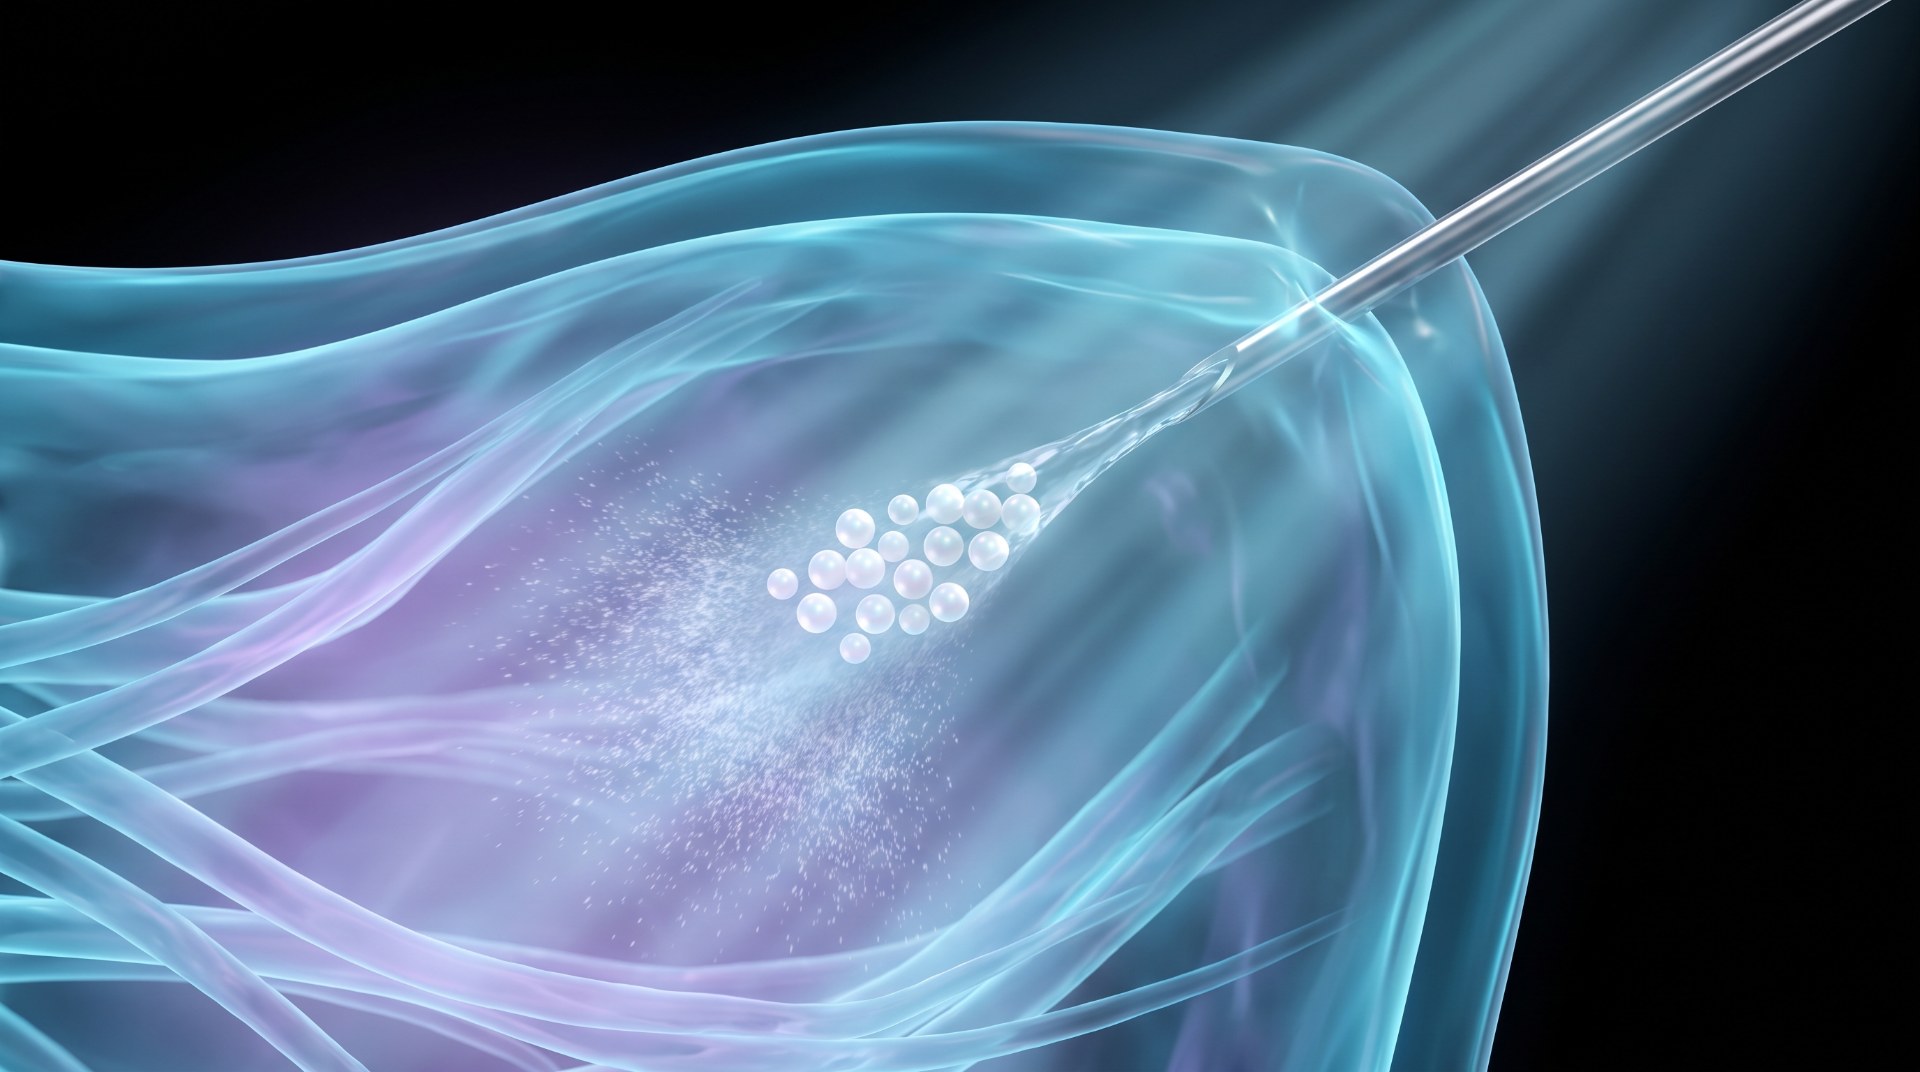
Suspend CaHA microspheres inside an HA gel and you get both: the lift you see today and the collagen you build for months.

SFERA Hybrid 30.5

One syringe. A fixed, engineered ratio.

3 mL premixed. Calcium hydroxylapatite and hyaluronic acid in one gel.

Hyaluronic acid2.1mL · 70%
CaHA0.9mL · 30%
Total3.0mL
Mechanism of action

Four stages, one syringe

01 · Day 0Placement & liftHA gel restores volume instantly and holds the microspheres in place.
02 · Early weeksHost responseA controlled, mild response recognises the microspheres and signals repair.
03 · Weeks to monthsFibroblast activationFibroblasts attach and stretch across the scaffold, laying down type III then type I collagen and elastin.
04 · MonthsRemodelingHA slowly resorbs as new tissue takes over. CaHA breaks down to calcium and phosphate.
Mechanism of action

The scaffold becomes the tissue

Each microsphere is a surface for fibroblasts to grip. Tension switches them back on, and the collagen they build stays after the gel is gone.

How HA and CaHA work on skin over time

The handover

Day 01 mo2 mo3 mo6 mo9 mo12 mo EFFECT HA · immediate volume, hydration CaHA · new collagen, firmness SFERA combined effect Fibroblasts activate Type I collagen builds HA largely resorbed

Illustrative curves based on CaHA and HA literature, not measured SFERA data.
How the effect hands over

From filler to tissue

Day 0HA gives immediate volume and lift
WeeksFibroblasts attach to the microspheres and activate
MonthsNew collagen matrix forms as HA slowly resorbs
Long termFirmer, thicker, better-quality skin
Why premixed matters

No mixing. No guessing.

  • Published hybrid work mostly mixes two products chair-side, with ratios that vary by injector
  • Authors cite lack of standardization as a source of variable outcomes
  • SFERA gives the same ratio in every syringe, every patient, every clinic
What the literature says about CaHA–HA hybrids
Braz et al. · PRS Global Open · 2024HA provides immediate lift; CaHA microspheres drive neocollagenesisPreclinical: higher lift capacity and faster tissue integration than CaHA alone, with collagen I expression.
Vitale et al. · J Craniofac Surg · 202546 patients, 12-month follow-up, cannula subdermalNatural reshaping with immediate and lasting results; no significant complications reported.
Lazzarotto et al. · JPRAS Open · 2026Premixed hybrid, subdermal mid and lower faceImproved aging severity and patient-perceived skin glow at 4 months; well tolerated.
Systematic review · Aesthetic Plast Surg · 2025High effectiveness and satisfactionMinor, self-resolving adverse effects. Authors call for longer, more rigorous trials.

Class evidence for CaHA–HA hybrids. Not SFERA-specific data.

Injection techniques

Match the technique to the goal

BolusNeedle · supraperiostealSmall deposits on bone for structure and projection.
Linear retrogradeCannula or needle · subdermalA thread of product while withdrawing. Lines, borders, jawline.
FanningCannula · subdermalRadiating passes from one entry point. Even coverage for skin quality.
Cross-hatchingCannula · subdermalTwo fanning layers at right angles. Laxity over larger areas.

Cannula preferred where anatomy allows. Inject slowly, low pressure, small aliquots, massage to spread evenly.

Injection levels

Every layer has a job

SubdermalSkin quality: fanning, cross-hatching with cannula
Deep fatVolume restoration in fat compartments
PeriosteumStructure and projection: small bolus with needle
AvoidIntradermal placement: risk of visible nodules
EPIDERMISDERMIS SUBDERMAL FATSMAS / MUSCLE DEEP FATPERIOSTEUM BONE
Safety first

Know the map before the needle

  • Respect the danger zones and the depth of each artery
  • Prefer a blunt cannula where anatomy allows; inject slowly, in small aliquots
  • Hyaluronidase reverses the HA phase only; the CaHA phase is not dissolvable
  • Have a written vascular occlusion protocol in every room

Choosing the right patient

Who benefits most

  • Volume loss plus early laxity or thin, crepey skin
  • Patients who want natural, progressive change
  • Avoid areas where CaHA is classically not used, such as lips and periorbital
  • Standard filler contraindications apply: active infection, pregnancy, autoimmune flares
Results to expect

What your patient will see

Day 0Visible lift and contour from the HA phase
4–6 weeksSkin starts to feel firmer as collagen forms
3 monthsThicker, more elastic skin with a natural glow
12 monthsHybrid series followed patients to one year with lasting results

Results vary by patient, area and technique. Based on CaHA–HA hybrid literature.

Session 01 · Face & Neck
Dr. Rehab Zakaria &
Dr. Nehal Helaly
Session 01 · What is SFERA

One gel. Two actives.

Hyaluronic acid
mg/mL
Crosslinked hyaluronic acid
+
Calcium hydroxylapatite microspheres
Calcium
CaHA microspheres
=
1syringe
Premixed · 3 mL

Immediate volume from HA. Lasting collagen from calcium.

Calcium hydroxylapatite · SFERA

CaHA

Smooth spheres

Uniform microspheres carried in a gel. Volume on day 0, then a scaffold that fibroblasts build on.
Poly-L-lactic acid

PLLA

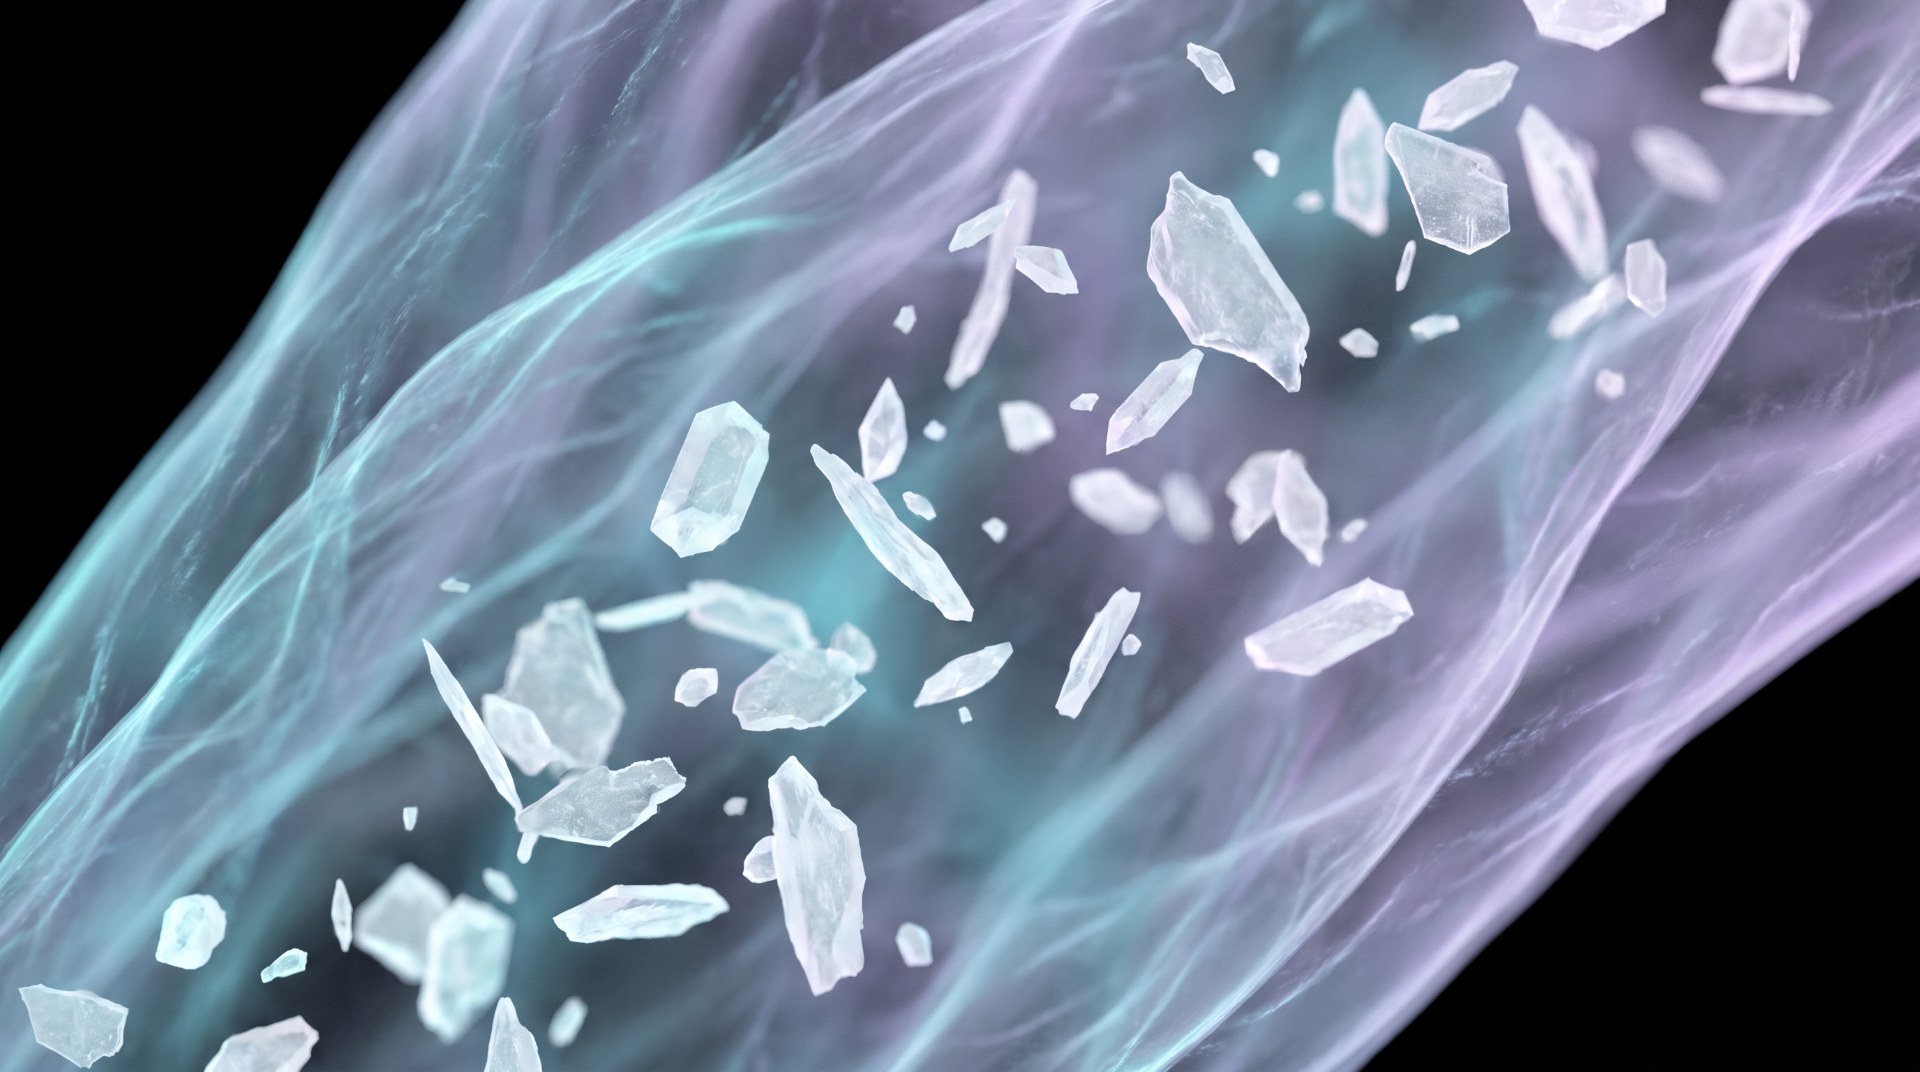
Irregular particles

Polymer fragments with no lasting carrier. No volume on day 0; collagen builds slowly through a mild inflammatory response.

Face & Neck · Two biostimulators

Same goal, different behaviour

CaHA vs PLLA at a glance

What changes in the clinic

CaHA · SFERA Hybrid
PLLA
ParticleSmooth, uniform microspheresIrregular polymer fragments
Day 0Immediate volume from the gel and the HA phaseNo lasting volume; the water carrier resorbs in days
CollagenType III from ~4 months, type I by ~9 monthsGradual, over 3–6 months
SessionsUsually one, review at 3 monthsTypically 2–3, weeks apart
PreparationReady in the syringe; dilute with saline for the jobReconstitute with sterile water and hydrate before use
BreakdownCalcium and phosphate ionsLactic acid, then CO₂ and water
Lifespan in tissueUp to ~2 years; fully resorbed by ~2.5About 2 years
ImagingVisible on CT, does not obscure or migrateNot visible
NodulesLower tendency with uniform spheres; most self-resolveHigher with irregular particles and low dilution

Class comparison from the CaHA and PLLA literature (McCarthy 2024, Kadouch 2017). Not head-to-head SFERA data.

Choosing the biostimulator

When SFERA, when PLLA

Choose SFERA when

  • The patient wants a visible result today and a better one in 3 months
  • You need contour and skin quality in one plan: jawline, chin, cheeks
  • Neck, décolleté and hands with one syringe, no reconstitution
  • The HA phase lets you adjust with hyaluronidase if needed

Consider PLLA when

  • Diffuse volume loss over large areas where a slow build is acceptable
  • The patient accepts 2–3 sessions and no change on day 0
  • High-volume body work such as buttocks or thighs
  • A result that should not be noticed as it builds

"I'm afraid it never goes away"

It goes. Completely. The collagen stays.

DAY 0Microspheres placed6 MONTHSCollagen forming12 MONTHSBreaking down18 MONTHSMostly gone24 MONTHSIons metabolised
~2.5 years · complete resorptionMicrospheres break down into calcium and phosphate ions
The evidence that it goes away

Four papers, one answer

Lemperle et al., Aesthetic Plastic Surgery 2003
Absorbed by 12 monthsTest deposits biopsied at 1, 3, 6 and 9 months: almost no foreign-body reaction, and the CaHA was absorbed by 12 months.
McCarthy et al., Aesthetic Surgery Journal 2024
Complete resorption within 2.5 yearsCaHA persists up to about 2 years, the carrier gel for months. Nodules never outlive the material.
Carruthers et al., Dermatologic Surgery 2008
No obscuring, no migration58 patients imaged with X-ray and CT: visible on CT, but underlying structures were never obscured and nothing migrated.
Kadouch, Journal of Cosmetic Dermatology 2017
3% adverse events in 5,081 treatments96% of those were nodules, mostly invisible and resolving without intervention.

Class evidence for calcium hydroxylapatite. Not SFERA-specific data.

What SFERA recommends

Dilute with saline for the job

Rejuvenation · skin quality3 mL SFERA + 5 mL saline
SFERA · 3 mLsaline · 5 mL = 8 mL · 1 : 1.7 Face, neck, décolleté, hands · superficial subdermal fanning
Face restructure · contour3 mL SFERA + 3 mL saline
SFERA · 3 mLsaline · 3 mL = 6 mL · 1 : 1 Jawline, chin, cheeks, temples · deeper placement for structure

Luer-to-luer connector · mix until homogeneous · inject slowly in small aliquots
The calcium question

Nodules: rare, mostly self-limiting

  • In 5,081 treatments, 3% had any adverse event; 96% of those were nodules, mostly invisible and resolving on their own
  • About half occurred in dynamic areas such as the lips: avoid them
  • Non-inflammatory nodules are product placed too superficially or too concentrated
  • Inflammatory nodules are red, tender and delayed: think infection, biofilm or hypersensitivity
  • No nodule outlives the material
Prevent it

How we inject

PlaneSubdermal or on bone. Never intradermal
Dilute5 mL saline for skin quality, 3 mL for structure
DeliverSmall aliquots, slow, low pressure, cannula where possible
FinishMassage to spread evenly. Do not overcorrect
AvoidLips, perioral, periorbital, glabella and any sphincteric muscle
EPIDERMISDERMISSUBDERMALMUSCLE INTRADERMAL · CONCENTRATEDclump, bump, nodule SUBDERMAL · DILUTED · SPREADeven, invisible, biostimulating
Treat it

The treatment ladder

0
Reassure and waitMost nodules resolve on their own and never outlive the product. Review at 4 weeks.
1
DisperseSaline or sterile water into the nodule, then firm massage. Add lidocaine for comfort. Hyaluronidase dissolves the HA phase of SFERA.
2
Intralesional therapyInflammatory or persistent: 5-FU with corticosteroid, under ultrasound guidance. Antibiotics if infection or biofilm is suspected.
3
RemoveLast resort: needle or blade extraction, or a micro-cannula under local anaesthesia.
!
Sodium thiosulfate: not recommendedPreclinical work shows it disperses rather than dissolves CaHA and carries a necrosis risk.
Algorithm adapted from McCarthy et al., Aesthetic Surg J 2024 and Danysz et al. 2020
Face & Neck

Contour that regenerates

  • Lift and contour from the HA phase: jawline, cheek, temple support
  • Skin quality from the CaHA phase: thickness, firmness, glow
  • One product for structure and surface
The neck

Thin skin, high demand

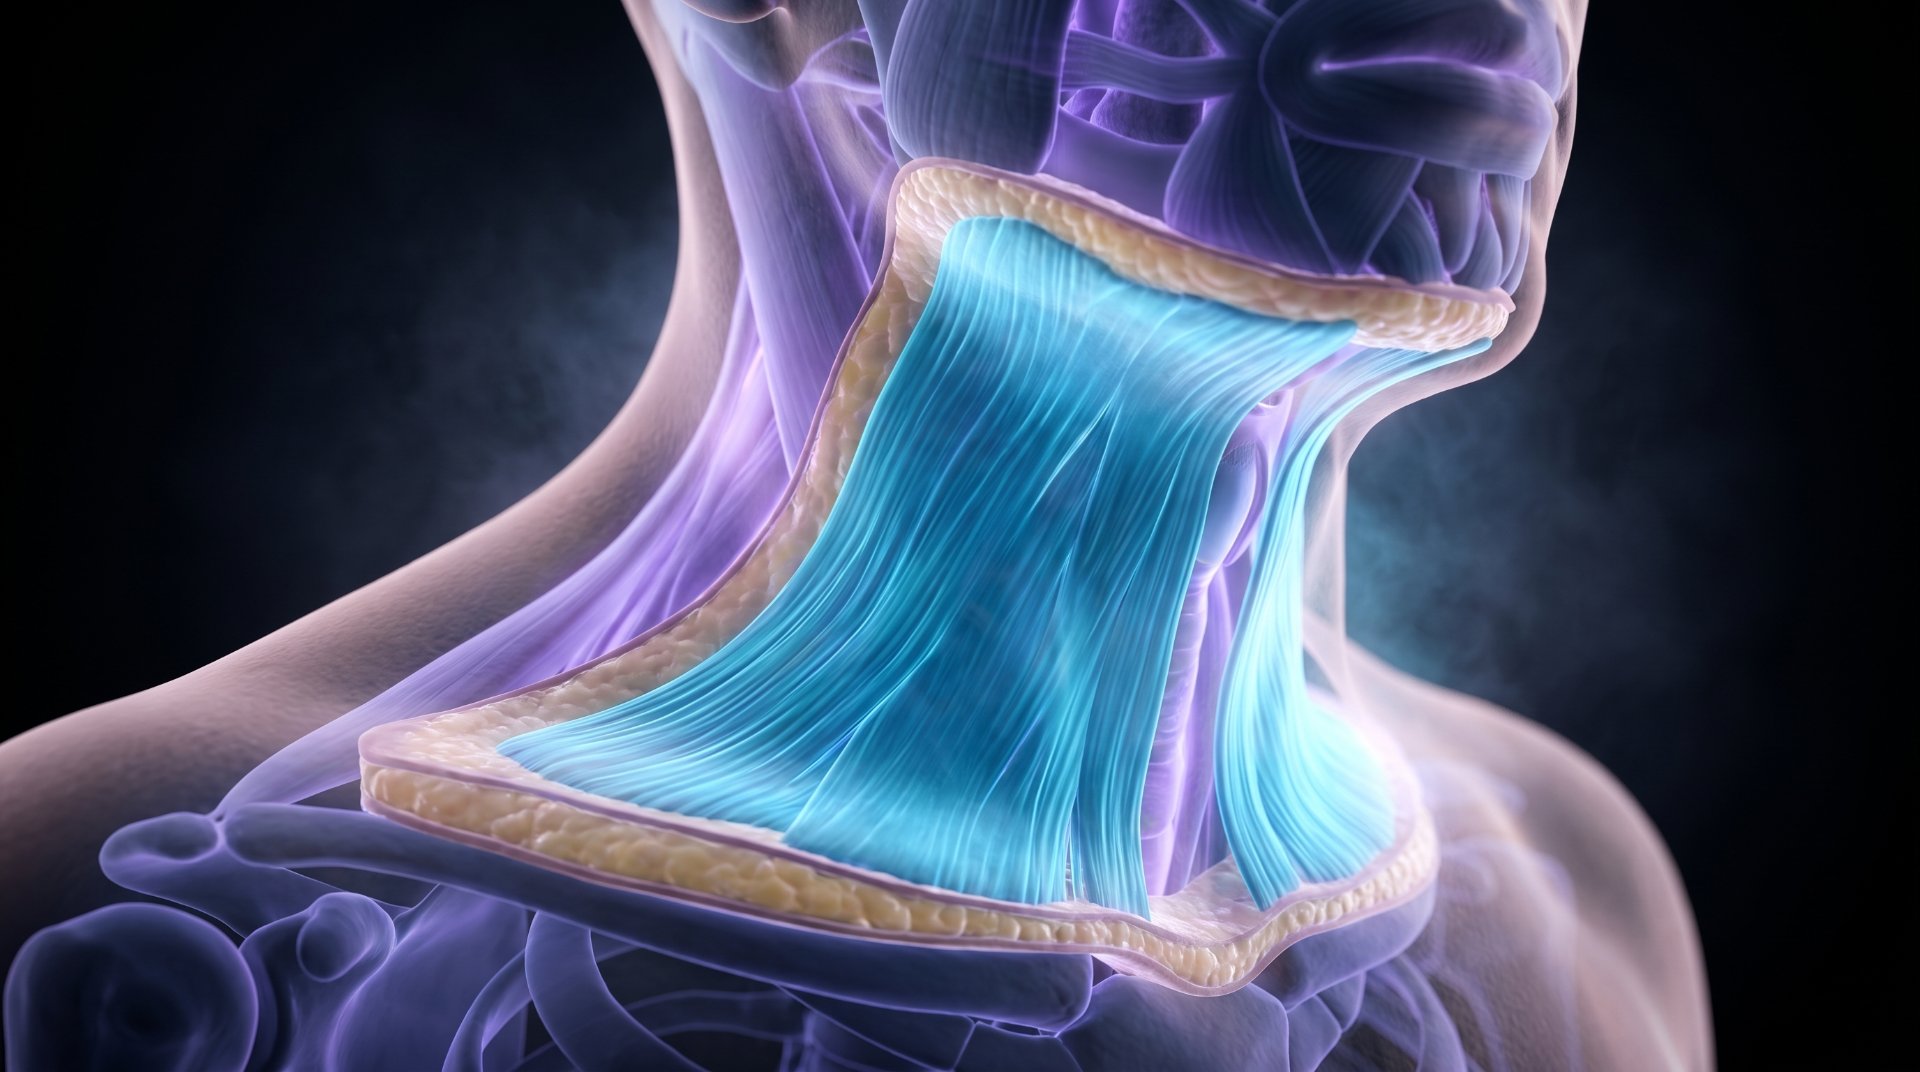
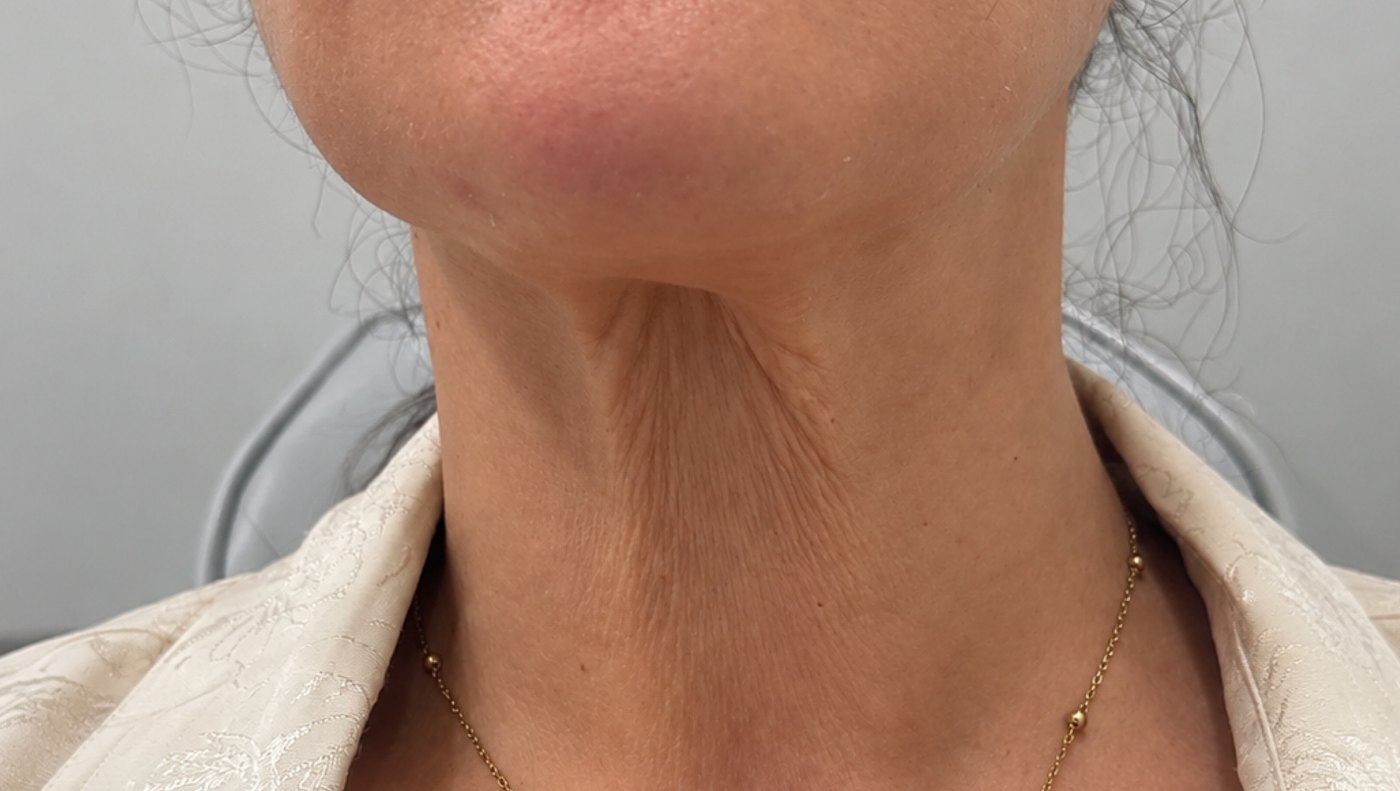
  • Thin dermis over the platysma shows every line
  • Biostimulation targets laxity and texture, not bulk
  • Superficial subdermal plane, fanning with a cannula

TEMPLE
Session 01 · Upper face

Upper face

DermisSubdermalFatMusclePeriosteum
1
TemplesSmall bolus on bone, deep to the temporalis, with a needle
2
Temple hollowAlternative: superficial subdermal fanning with a cannula from a lateral entry
3
Stay clearGlabella, periorbital area, supraorbital and temporal vessels
StructureSkin qualityDanger zoneCannula path
ZYGOMASUBMALAR
Session 01 · Mid face

Mid face

DermisSubdermalFatMusclePeriosteum
1
Cheek structureBolus on the zygomatic arch and lateral cheek with a needle
2
Submalar hollowSubdermal fanning with a cannula from a lateral entry
3
Stay clearTear trough, infraorbital foramen, nasolabial vessels
StructureSkin qualityDanger zoneCannula path
ANGLECHIN
Session 01 · Lower face

Lower face

DermisSubdermalFatMusclePeriosteum
1
Angle and chinBolus on bone with a needle for definition and projection
2
JawlineLinear retrograde threads along the mandibular border with a cannula
3
Stay clearLips, facial artery at the antegonial notch, mental foramen
StructureSkin qualityDanger zoneCannula path
SKIN QUALITY
Session 01 · Neck

The neck

DermisSubdermalFatMusclePeriosteum
1
Entry pointsLateral neck on each side, cannula only
2
FanningSuperficial subdermal passes across horizontal lines and lax skin
3
Stay clearDeep plane, midline thyroid area, platysmal bands
StructureSkin qualityDanger zoneCannula path
AfterBefore
ILLUSTRATIVE SIMULATION · NOT PATIENT RESULTS
Before we inject · Face & Neck

What happens in this area over time

Day 0Visible lift and contour from the HA phase
4–6 weeksFibroblasts activate; skin begins to feel firmer
3 monthsThicker skin, sharper jawline, smoother neck
12 monthsResults maintained; review and plan top-up
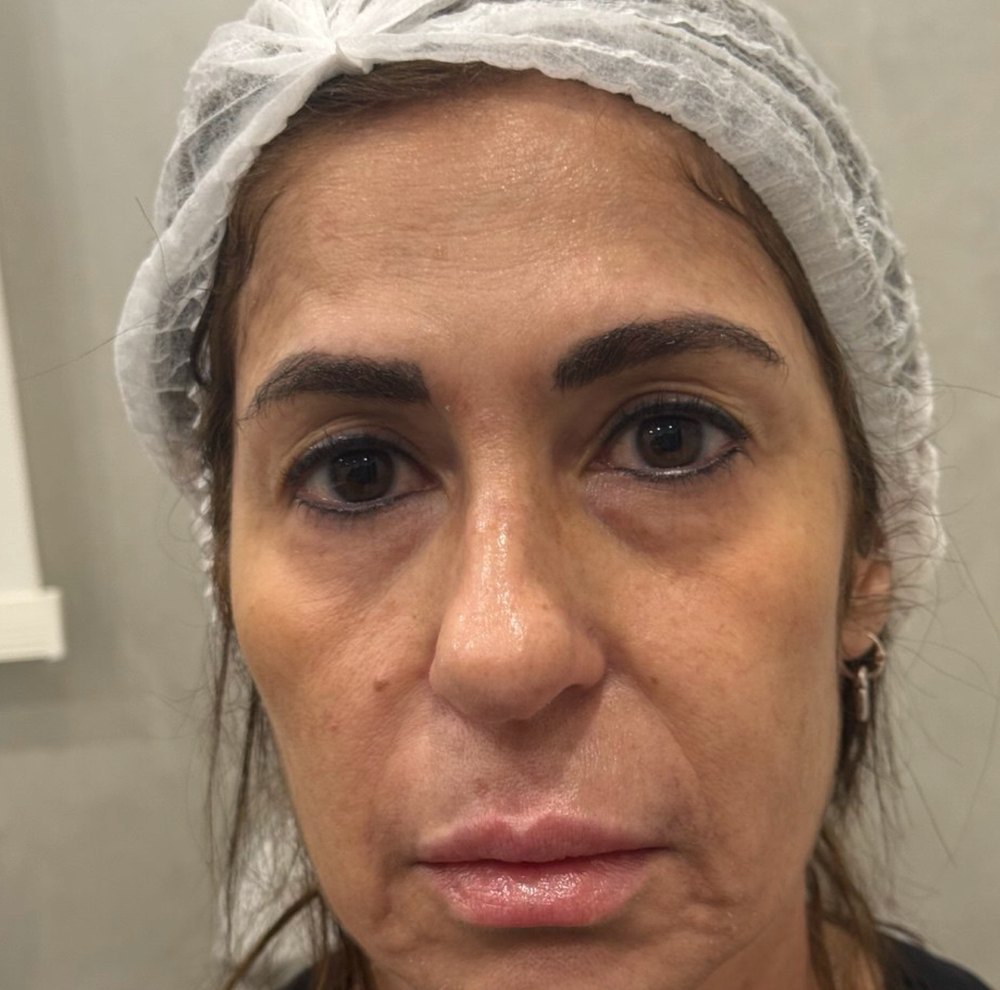
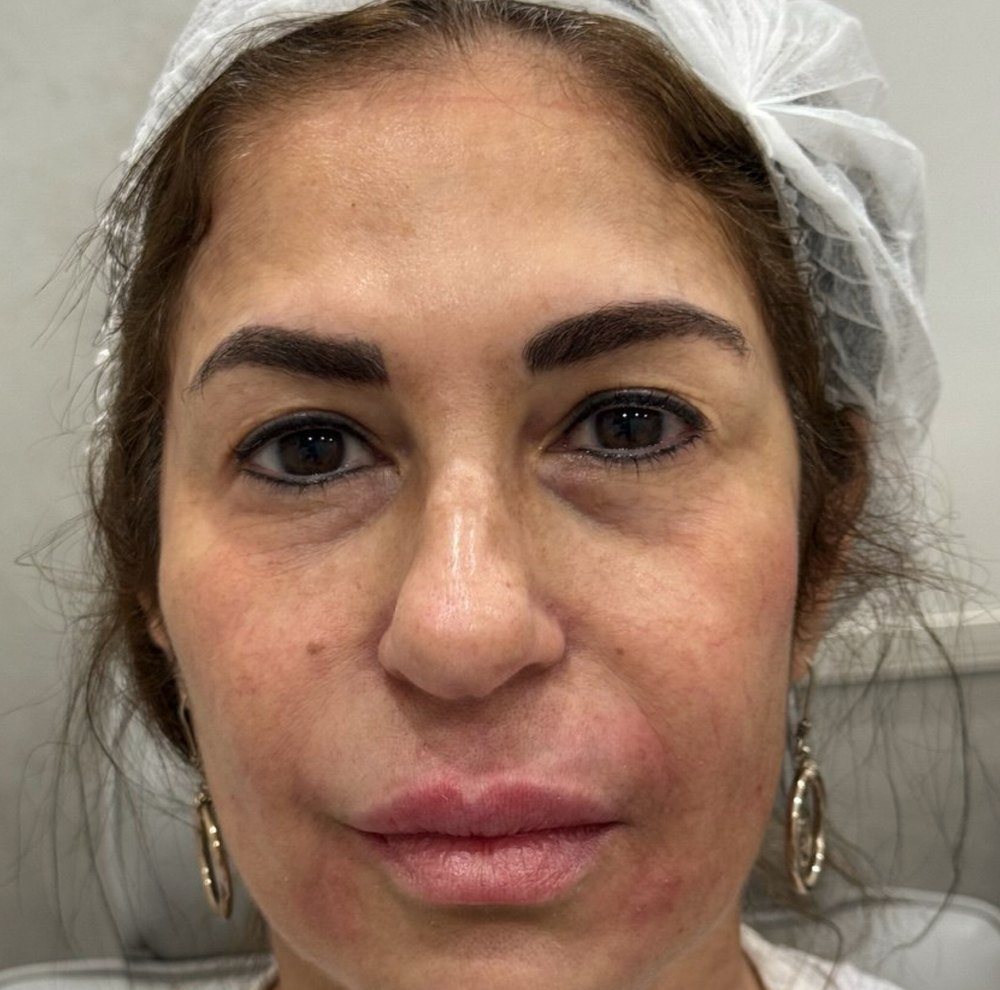
Real patient results · Face · Dr. Rehab Zakaria

Full-face skin quality

01/ 03
BeforeBefore
AfterAfter
→
  • Brighter, more even skin tone and texture
  • Softer tear-trough and mid-face shadows
  • Smoother peri-oral area and lip frame
SFERA Hybrid 30.5 · Clinical case
Photos courtesy of Dr. Rehab Zakaria · Individual results vary
Real patient results · Face · Dr. Rehab Zakaria

Lower face · contour

02/ 03
BeforeBefore
AfterAfter
→
  • Softer nasolabial and marionette shadows
  • More defined jawline and chin transition
  • Overall glow and hydration
SFERA Hybrid 30.5 · Clinical case
Photos courtesy of Dr. Rehab Zakaria · Individual results vary
Real patient results · Neck · Dr. Rehab Zakaria

The neck · texture & laxity

03/ 03
BeforeBefore
AfterAfter
→
  • Horizontal neck lines visibly softened
  • Tighter, smoother skin surface
  • Natural transition to the décolleté
SFERA Hybrid 30.5 · Clinical case
Photos courtesy of Dr. Rehab Zakaria · Individual results vary
Session 02 · Hands
Dr. Ayman Helmi
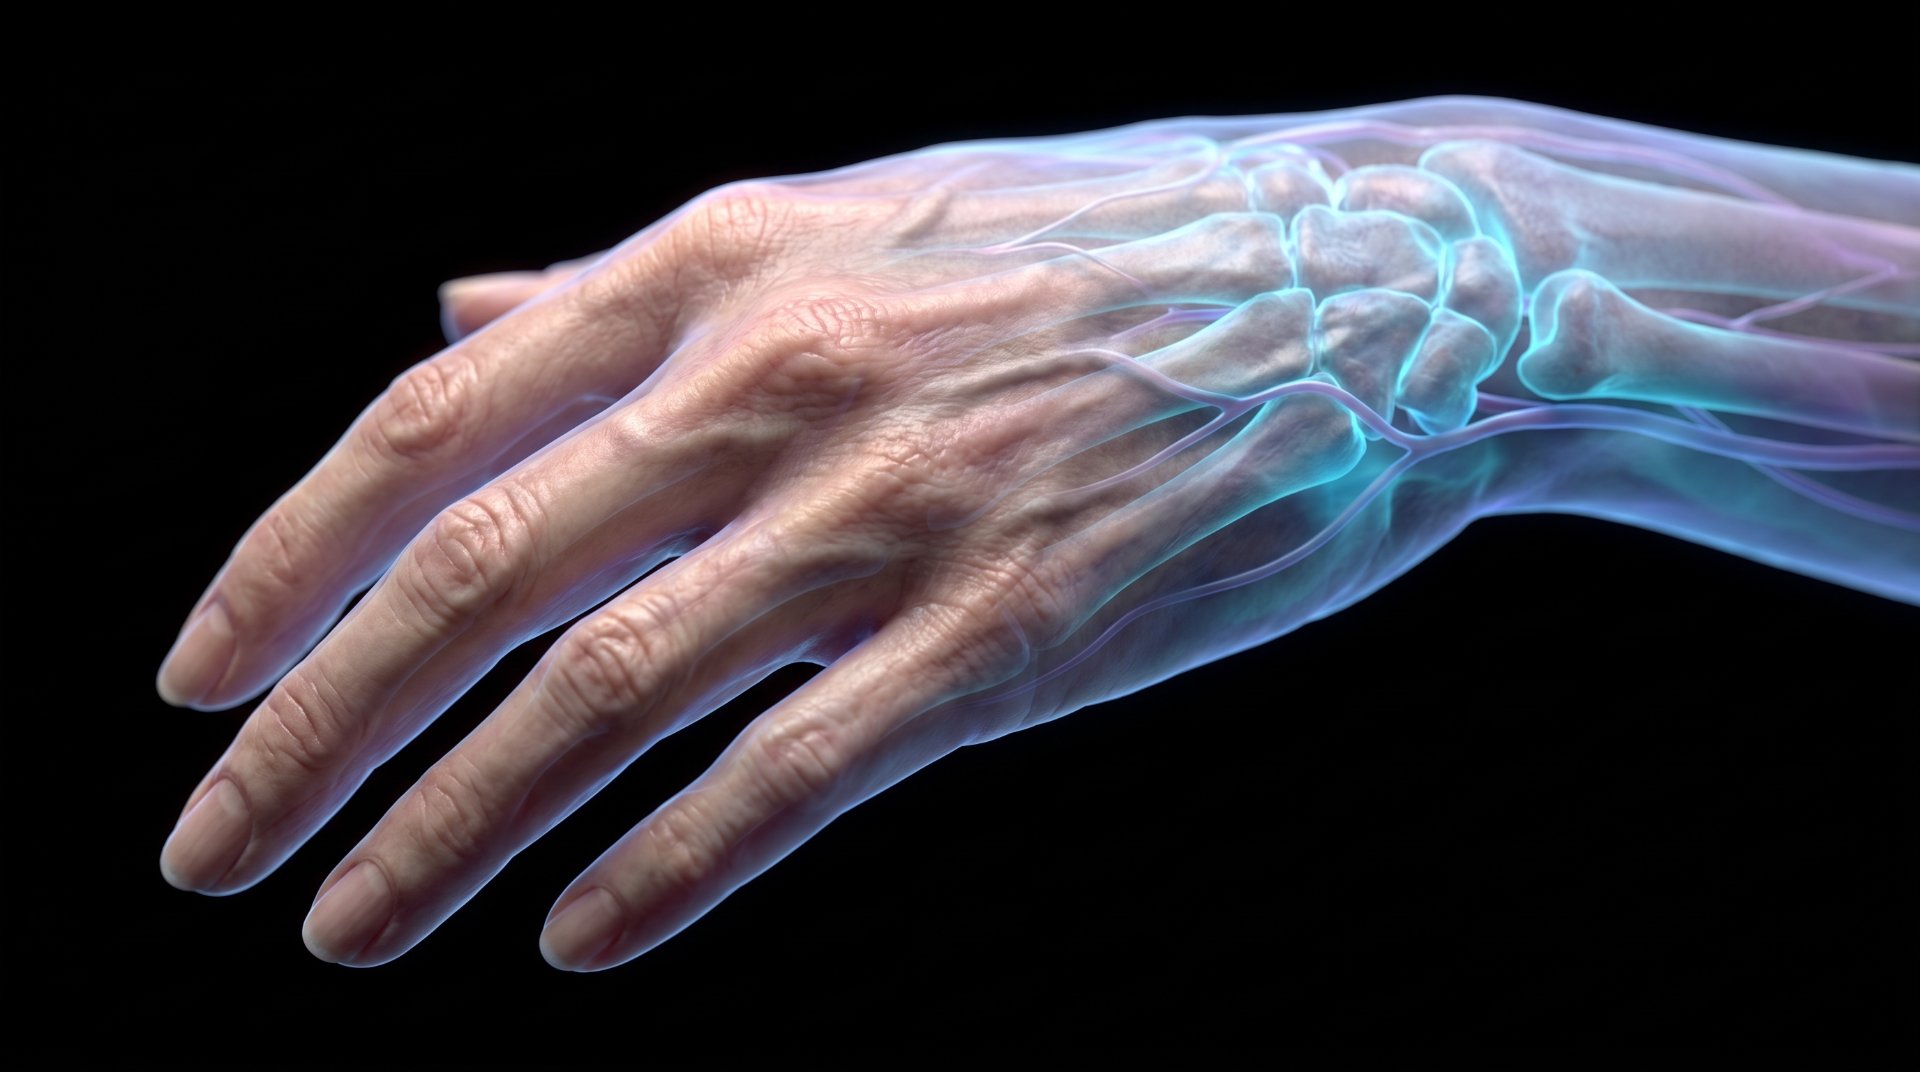
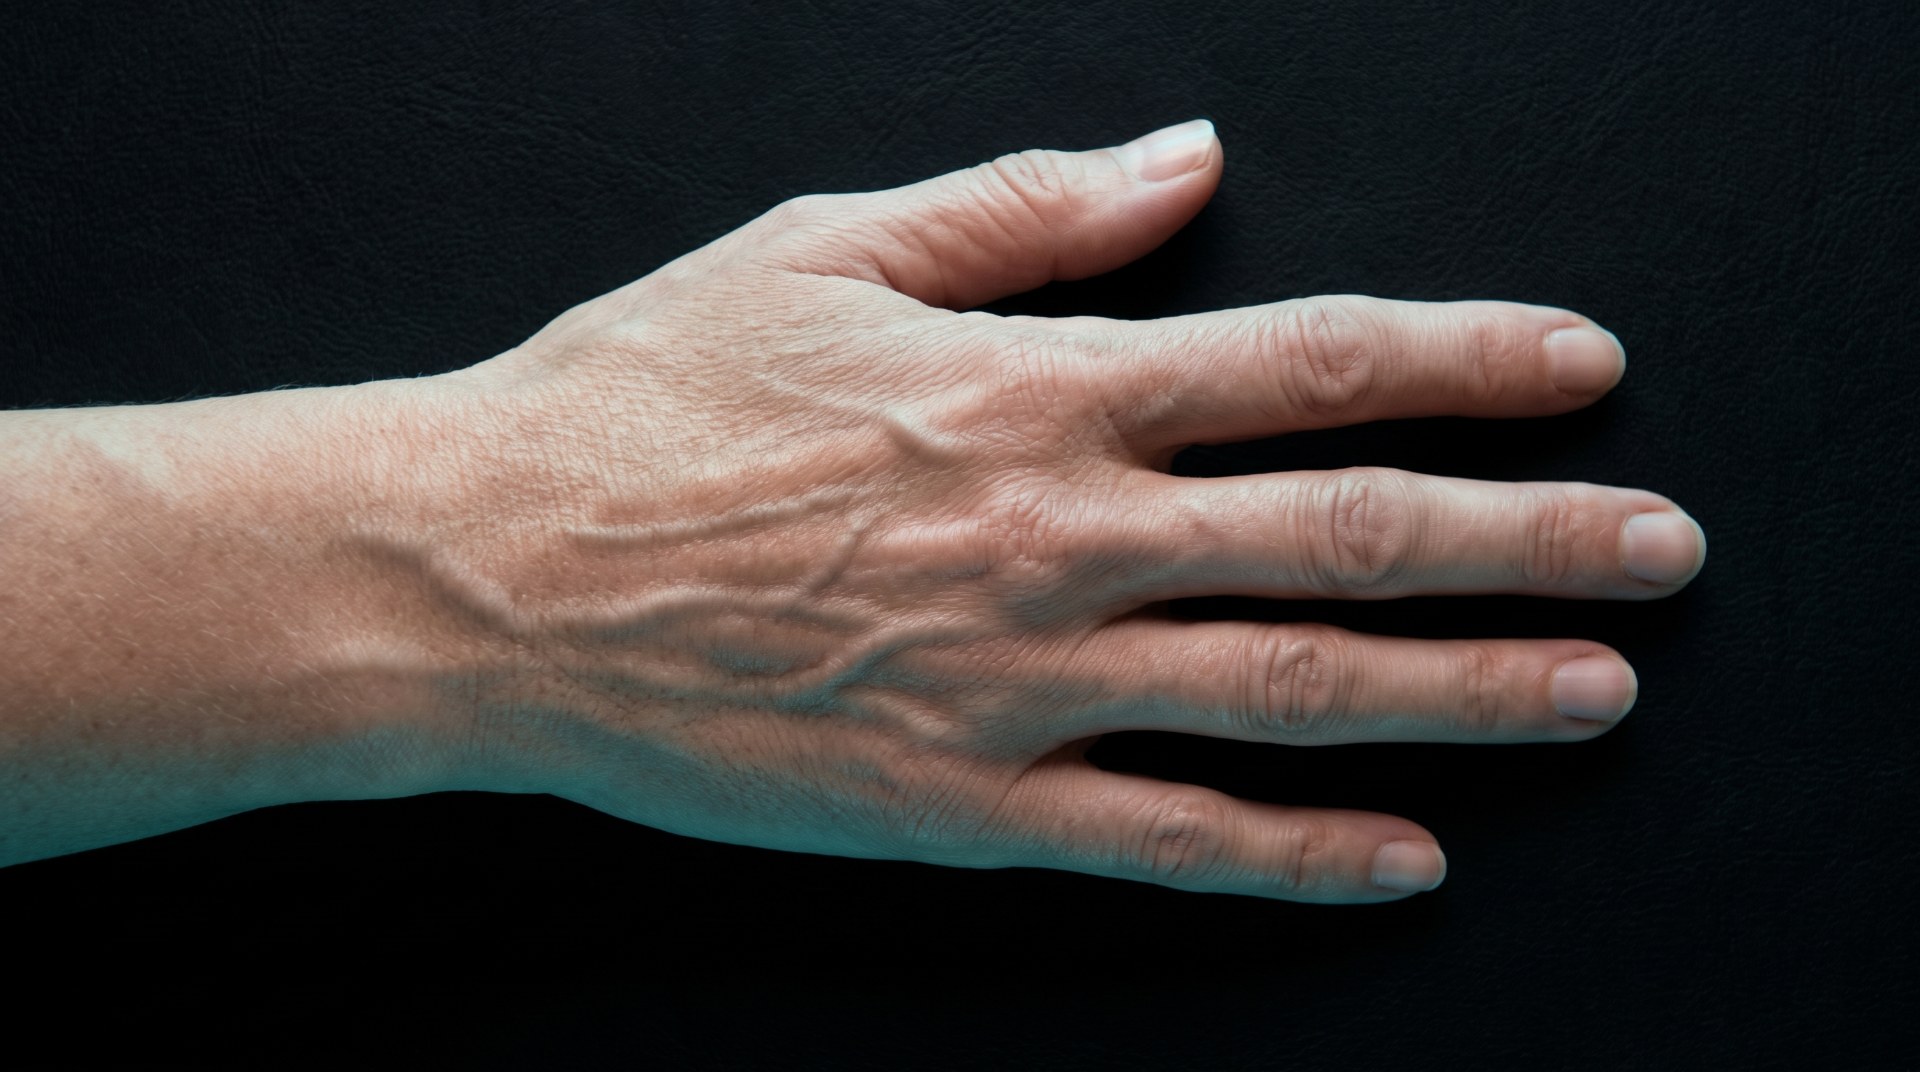
The aging hand

The hand tells the age

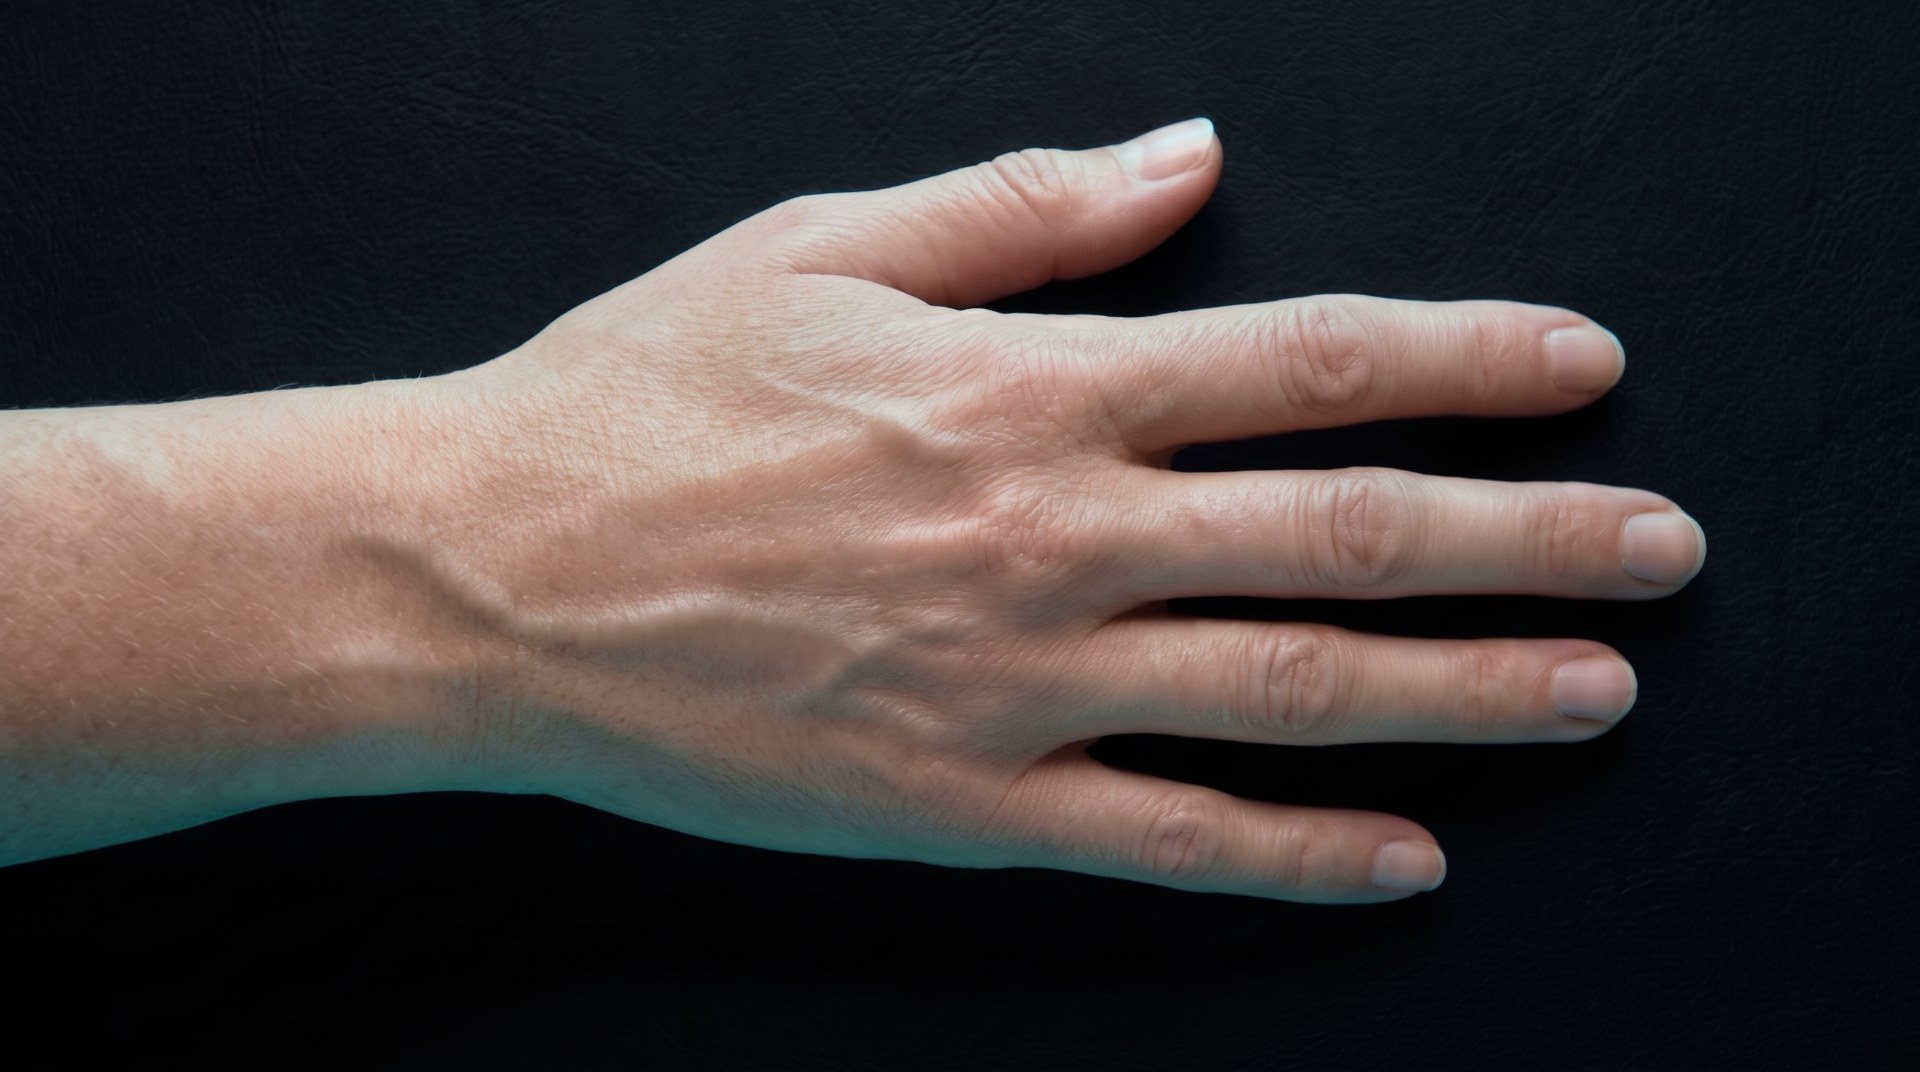
  • Fat loss exposes tendons and veins
  • Thin, translucent, crepey skin
  • Often left untreated while the face is rejuvenated
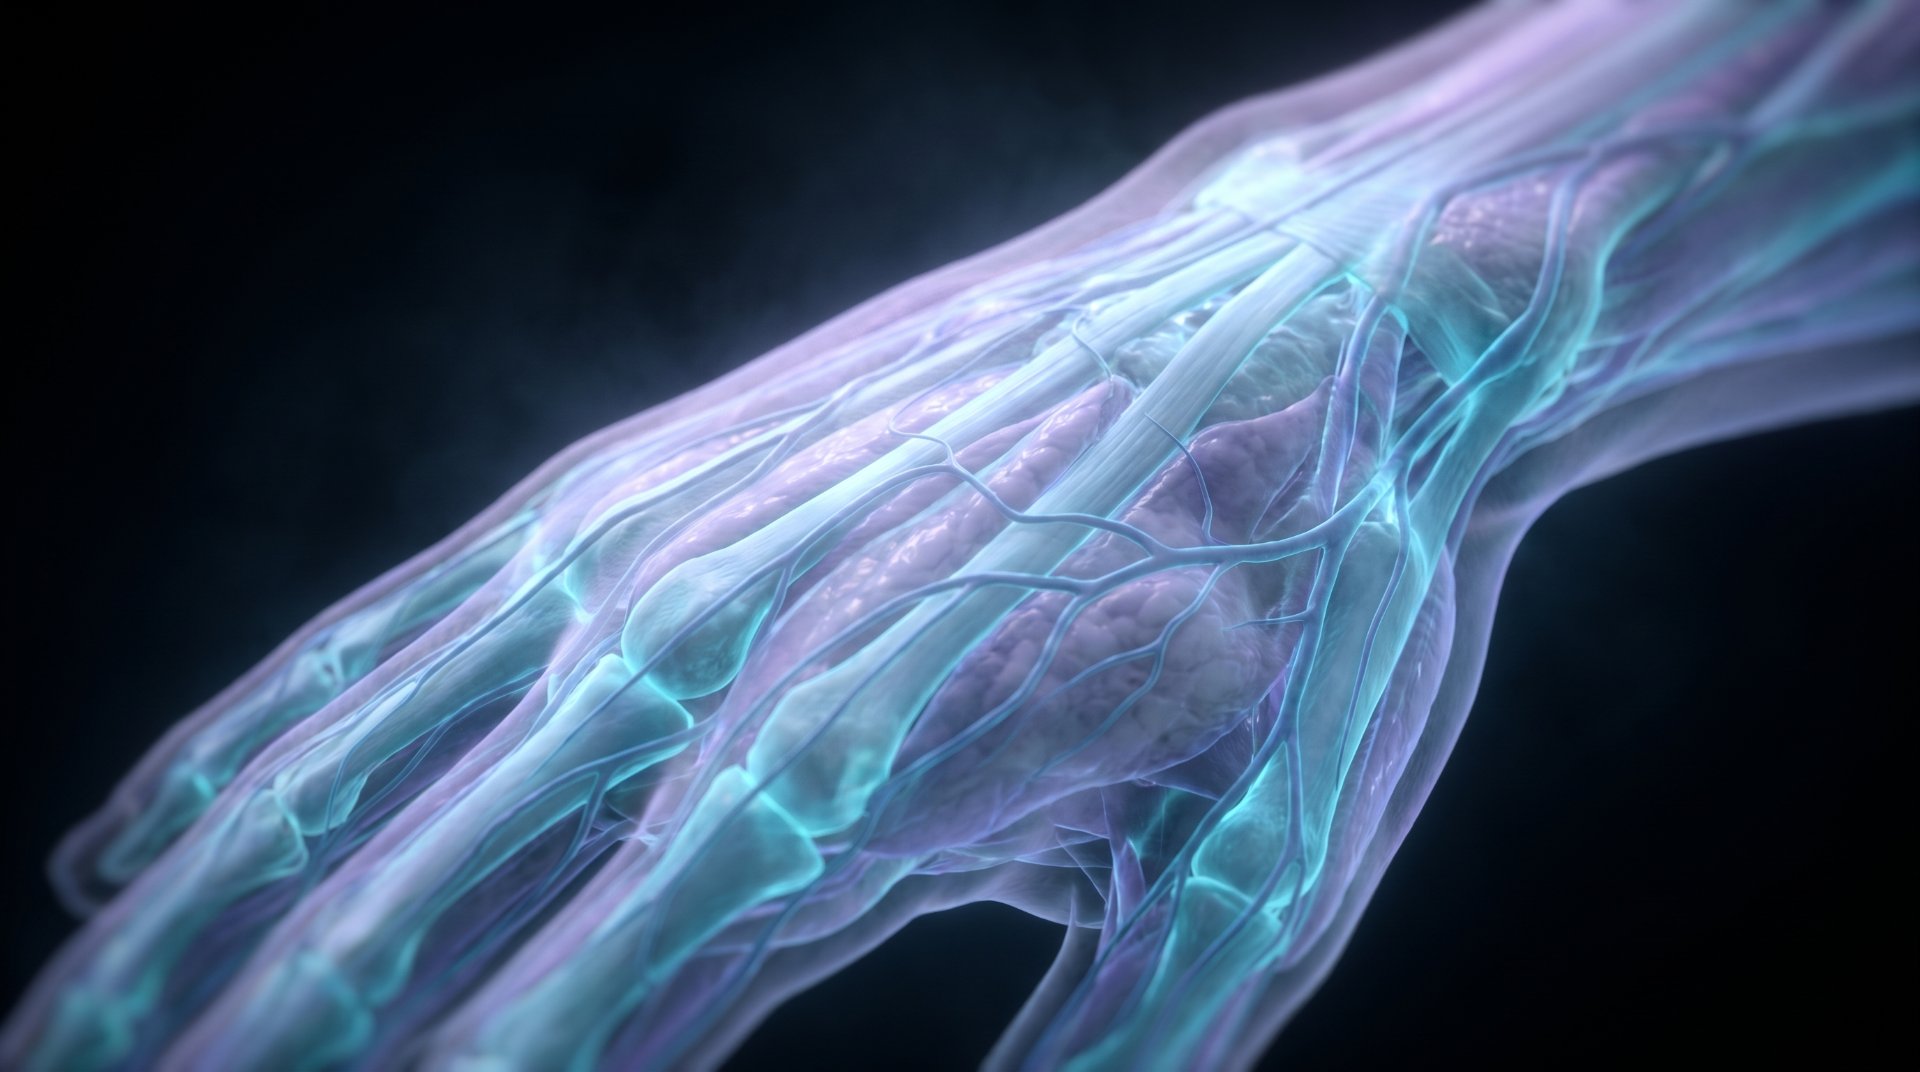
Hand anatomy

Work in the right layer

  • Dorsal hand has thin fatty laminae over tendons and veins
  • Target the plane superficial to tendons, below the dermis
  • Even distribution and gentle massage for a smooth result

Hand rejuvenation

Volume back. Skin renewed.

HA restores the lost volume that hides tendons and veins. CaHA keeps improving skin thickness long after.
INTERMETACARPAL SPACES
Session 02 · Hands

Dorsal hand

DermisSubdermalFatMusclePeriosteum
1
EntryNear the wrist, between the tendons
2
PlacementSubdermal fanning across the intermetacarpal spaces, or a bolus then massage
3
Stay clearDorsal veins and tendons; never inject deep
StructureSkin qualityDanger zoneCannula path
AfterBefore
ILLUSTRATIVE SIMULATION · NOT PATIENT RESULTS
Before we inject · Hands

What happens in this area over time

Day 0Volume restored; veins and tendons less visible
4–6 weeksCollagen building; skin feels thicker
3 monthsSmoother, plumper, more even hands
12 monthsResults maintained; review and plan top-up
Session 03 · Body Skin
Dr. Karim Aggour
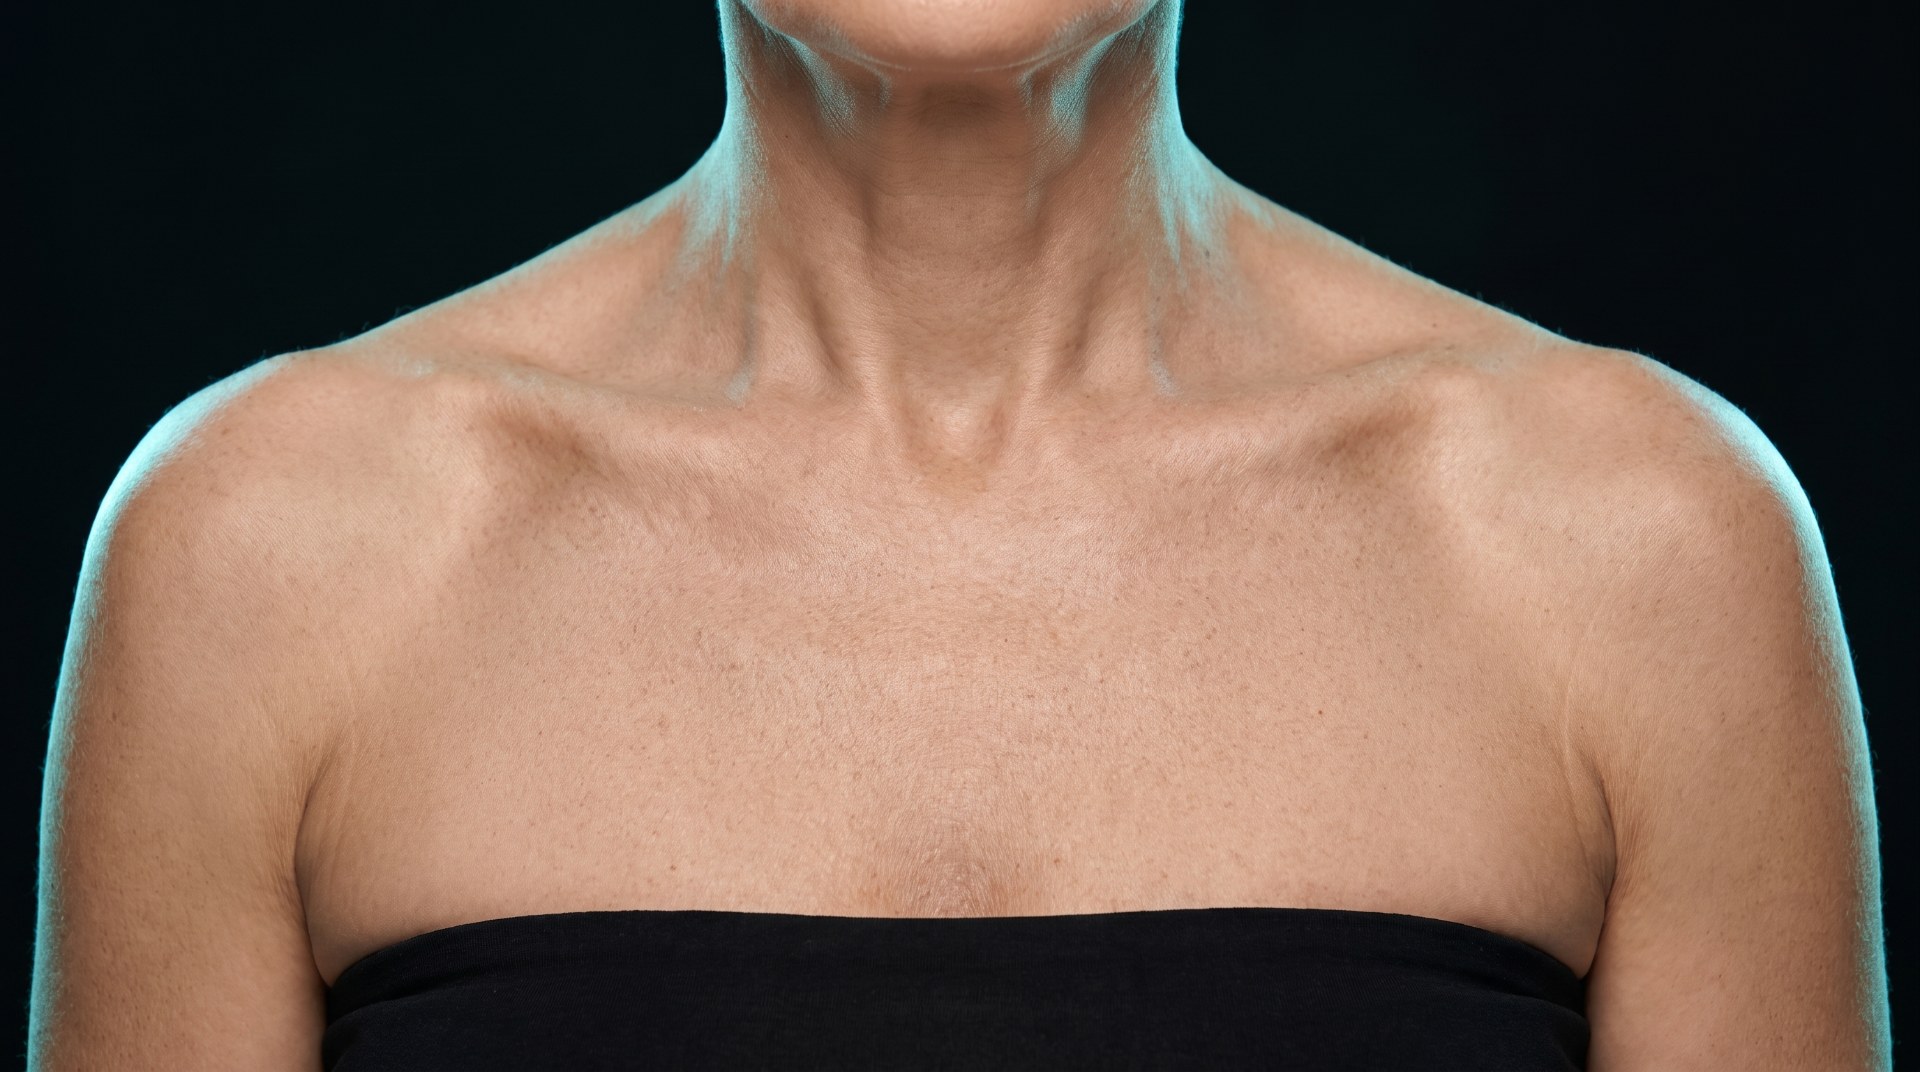
Décolleté

Crepey skin, restored

  • Sun damage and thin dermis create fine vertical lines
  • Goal: skin quality, never volume
  • Superficial, even distribution across the area
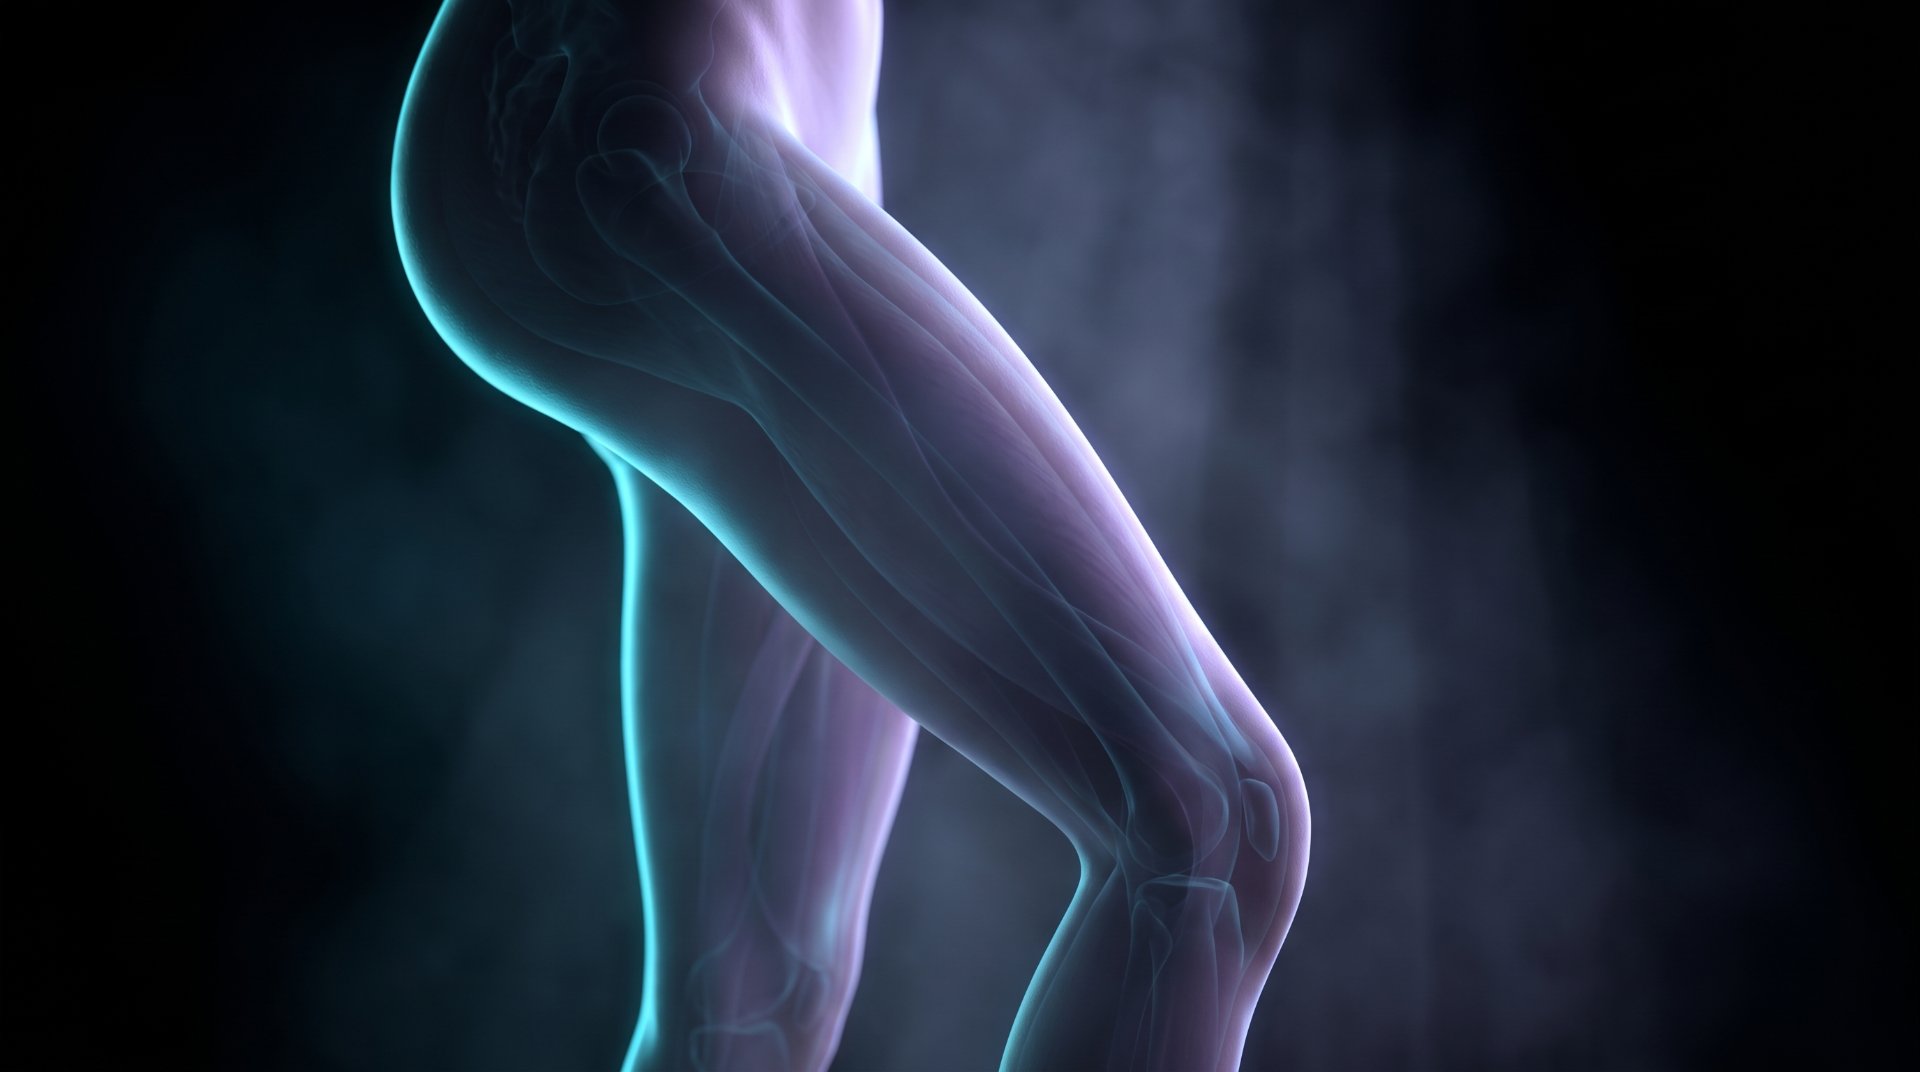
Thighs · cellulite

Smoother, firmer thighs

  • Cellulite dimpling from thin dermis and weak connective septae
  • New collagen thickens the dermis so dimples show less
  • Same technique firms lax body skin: arms, abdomen, knees

Body skin quality

Build the matrix back

On the body, SFERA works as a skin regenerator. The result is denser, firmer dermis that keeps improving for months.
SKIN QUALITY
Session 03 · Décolleté

Décolleté

DermisSubdermalFatMusclePeriosteum
1
Entry pointsTwo lateral points below the clavicles
2
Cross-hatchingTwo layers of subdermal fanning at right angles
3
Stay clearDeep plane, the sternal midline, breast tissue
StructureSkin qualityDanger zoneCannula path
CELLULITEFIRMNESS
Session 03 · Thighs & body

Cellulite & firmness

DermisSubdermalFatMusclePeriosteum
1
Map the dimplesMark the cellulite area standing, before lying down
2
Grid techniqueSubdermal cross-hatching with a cannula over the marked area
3
Stay clearDeep or intramuscular injection, the saphenous vein course
StructureSkin qualityDanger zoneCannula path
AfterBefore
ILLUSTRATIVE SIMULATION · NOT PATIENT RESULTS
Before we inject · Body

What happens in this area over time

Day 0Little visible change; this is a skin quality treatment
4–6 weeksEarly firmness as collagen forms
3 monthsFirmer skin; dimples and crepey texture less visible
12 monthsResults maintained; assess for a repeat session
Take home

One syringe. Two actions.

  • HA for immediate lift and hydration
  • CaHA for collagen that keeps building
  • Premixed 0.9 : 2.1 for a result you can repeat
  • Face, neck, hands, body with one hybrid

Thank you
← → navigate · F fullscreen